Management of Hip Fractures in the Elderly
| Site: | EHC | Egyptian Health Council |
| Course: | Orthopedics Guidelines |
| Book: | Management of Hip Fractures in the Elderly |
| Printed by: | Guest user |
| Date: | Sunday, 20 September 2026, 9:43 PM |
Description
"last update: 10 September 2026" Download Guideline
- Executive summary
|
Recommendations |
|
1. Imaging 1.1. In adults with clinical suspicion of hip fracture but adequate quality negative standard X-rays (anteroposterior pelvis and lateral hip), cross-sectional imaging should be performed. Specifically: 1.1.1. Magnetic resonance imaging (MRI) is the preferred modality due to higher diagnostic sensitivity and specificity for occult hip fractures. (Strong recommendation) 1.1.2. Computed tomography (CT) should be considered when MRI is unavailable within 24 hours, contraindicated, or impractical. (Conditional Recommendation) 1.1.3. If CT is used first and is negative despite ongoing clinical suspicion, MRI should subsequently be obtained to rule out occult fracture (unless contraindicated). (Strong Recommendation). 2. Preoperative traction 2.1. We advise against the routine use of preoperative traction for patients with a hip fracture. (Conditional recommendation) 3. Timing of surgery 3.1. Perform hip fracture surgery on the day of, or the day after admission to hospital (within 48 hours); taking into consideration the patient optimization for surgery. (Conditional recommendation) 4. Antithrombotic Management 4.1. On admission, confirm the antithrombotic agent(s), last dose time, renal function and indication (VTE prophylaxis vs therapeutic anticoagulation) before committing to neuraxial or deep regional techniques. (Strong recommendation) 4.2. If surgery is delayed beyond the day of admission, consider pharmacological VTE prophylaxis if VTE risk outweighs bleeding risk. Ensure the last dose is at least 12 hours before surgery for low dose LMWH and at least 24 hours for high dose LMWH and fondaparinux. (Strong recommendation) 4.3. Treat deep (non-compressible) nerve blocks like lumbar plexus or paravertebral blocks, the same way as neuraxial blocks in respect to VTE prophylaxis drugs interruption timing. For superficial (compressible) single-shot blocks like femoral nerve or fascia iliaca plane blocks, apply a site-based bleeding risk assessment and proceed when the expected benefit outweighs bleeding risk. (Strong recommendation) 4.4. Use Annex 2: Minimum interruption intervals (summary table) for a consolidated table. Key principles: 4.4.1. Dose intensity and renal function matter for LMWH and DOACs; insertion and removal of neuraxial catheters are both timing events (Strong recommendation) 4.4.2. It is advised to check platelet count if LMWH has been used for more than 4 days due to heparin-induced thrombocytopenia risk. (Conditional recommendation). 4.5. When neuraxial or deep catheters are used, coordinate LMWH dosing with both catheter placement and removal. 4.5.1. Stop low-dose LMWH at least 12 hours before placement or removal of the catheter, and for 24 hours before placement or removal in case of high dose LMWH. (Strong recommendation) 4.5.2. In all cases; (low and high dose LMWH); start first LMWH dose at least 12 hours after placement and at least 4 hours after removal. (Strong recommendation) 4.6. Provide post-operative VTE prophylaxis according to individual risk assessment; extended prophylaxis (e.g., 28–35 days) is commonly used after hip fracture surgery. (Conditional recommendation) 5. Perioperative Analgesia 5.1. Assess pain score immediately on presentation (at rest and on movement) and reassess within 30 minutes after any analgesic intervention; then hourly until pain is controlled, and thereafter with routine observations. (Strong recommendation) 5.2. Offer regular paracetamol/acetaminophen every 6 hours pre- and post-operatively unless contraindicated; use intravenous dosing when oral administration is unreliable. (Strong Recommendation) 5.3. Use opioids as rescue therapy with small, titrated doses (prefer immediate-release oral or carefully titrated IV boluses) when paracetamol alone is insufficient. Avoid initiating prolonged-release opioids in the acute perioperative phase. (Strong recommendation) 5.4. Offer an early peripheral nerve block [e.g., fascia iliaca, femoral, or Pericapsular Nerve Group (PENG)] block when trained staff and ultrasound are available, to improve pain control and reduce systemic opioid requirements. Do not delay surgery for block placement. (Conditional recommendation) 5.5. When opioids are used, prescribe antiemetic and bowel regimen, monitor sedation score, respiratory rate, and oxygen saturation, and screen for delirium daily. Encourage early mobilization and physiotherapy when clinically appropriate. (Strong recommendation) 5.6. Avoid routine NSAIDs/COX-2 inhibitors in frail older hip fracture patients. Consider them only when a senior clinician documents a favourable risk-benefit assessment and there are no contraindications (renal dysfunction, high bleeding risk, active GI disease, interacting anticoagulants). (Conditional recommendation) 5.7. Routine use of epidural analgesia for hip fracture surgery is discouraged. If used, restrict to selected cases under acute pain service or senior anaesthesia oversight, with explicit anticoagulant coordination and haemodynamic monitoring. (Conditional recommendation) 5.8. Use a layered multimodal regimen for all hip fracture patients unless contraindicated: regular paracetamol (acetaminophen) as baseline therapy, early peripheral nerve block (single-shot fascia iliaca or femoral nerve block where available), and opioids for rescue analgesia using small, titrated immediate-release doses. Reserve short-course NSAID/COX-2 inhibitor only in carefully selected low-risk patients (Strong recommendation) 6. Anaesthetic management 6.1. Proceed to surgery as soon as feasible once immediately reversible problems are addressed (e.g., hypoxia, hypovolaemia, severe electrolyte derangements, uncontrolled pain). (Strong Recommendation) 6.2. Either neuraxial (spinal) or general anaesthesia is acceptable. Choose the technique that can be delivered safely and promptly given antithrombotic timing, physiological reserve, airway risk, expected surgical duration, and local expertise. (Conditional recommendation) 6.3. Aim to maintain any change in systolic blood pressure/mean arterial pressure within approximately 20% of the patient’s baseline, avoid hypoxia and hypercarbia, maintain normothermia, and use a proactive vasopressor strategy with judicious fluids. (Strong recommendation) 6.4. For cemented arthroplasty, identify high-risk patients and apply BCIS (Bone Cement Implantation Syndrome) precautions: a team 'cement pause', maintain blood pressure close to baseline, optimize oxygenation, and have vasopressors immediately available. (Strong Recommendation) 6.5. Implement multimodal analgesia, delirium prevention measures (adequate pain control, oxygenation, hydration, sleep-wake support), and early mobilization. Coordinate VTE prophylaxis timing with any neuraxial or deep catheter use. (Strong recommendation) 7. Planning the theatre team 7.1. Schedule hip fracture surgery on a planned trauma list 7.2. Consultants or senior staff must supervise trainees and junior members of the anaesthesia, surgical, and theatre teams when they carry out hip fracture procedures (Good practice statement). 8. Surgical Procedures 8.1. Stable femoral neck fractures 8.1.1. In patients with stable femoral neck fractures (impacted/non-displaced, Garden’s I and II, Annex 6: Garden Classification of Femoral Neck Fracture), internal fixation or arthroplasty may be considered, after assessment of the patient and imaging of the hip joint. (Conditional recommendation) 8.2. Unstable femoral neck fractures 8.2.1. Arthroplasty vs Fixation 8.2.1.1. For displaced (Garden III/IV) fractures neck femur in ambulatory or functionally independent elderly patient, HA or THA is strongly recommended over internal fixation. (Strong Recommendation) 8.2.2. Unipolar/bipolar hemiarthroplasty 8.2.2.1. Use a femoral stem design other than Austin Moore or Thompson stems for arthroplasties. Unipolar (Austin Moore or Thompson) prosthesis should be used in strictly limited conditions, e. g. Unavailable bipolar prosthesis. (Good practice statement) 8.2.3. Total Arthroplasty vs Hemi Arthroplasty 8.2.3.1. For fit, active elderly patients (≥60 years) with displaced femoral neck fractures, Total Hip Arthroplasty (THA) is suggested rather than Hemiarthroplasty (HA) to improve function and reduce revision risk. (Conditional recommendation) 8.2.3.2. For frail, medically complex, or cognitively impaired patients with limited mobility, Hemiarthroplasty (HA) may be preferred due to shorter operative time and reduced perioperative risk. (Conditional recommendation) 8.2.3.3. Decisions should incorporate individual patient comorbidities, cognition, pre-fracture mobility, surgical risk, and patient preference. (Strong recommendation) 8.2.4. Cemented femoral stems 8.2.4.1. Cemented stem implants are preferred in patients undergoing surgery with arthroplasty. (Conditional recommendation) 8.2.5. Surgical approach 8.2.5.1. In patients undergoing treatment of femoral neck fractures with hip arthroplasty, evidence does not show a favoured surgical approach. Select approach based on surgeon’s experience and preference. (Good practice statement) 8.3. Intertrochanteric fractures 8.3.1. In patients with stable intertrochanteric fractures, use of either a sliding hip screw or a cephalomedullary device is recommended. Use a dynamic hip screw (DHS) in preference to an intramedullary nail in patients with stable intertrochanteric fractures (Strong recommendation) 8.3.2. In patients with unstable intertrochanteric fractures, the use of cephalomedullary device is recommended. (Strong recommendation) 8.3.3. In patients with subtrochanteric or reverse obliquity fractures a cephalomedullary device is recommended. (Strong recommendation) 9. Blood transfusion 9.1. A blood transfusion threshold of no higher than 8g/dl is suggested in asymptomatic postoperative hip fracture patients. (Conditional recommendation) 10. Tranexamic acid 10.1. Tranexamic acid should be administered to reduce blood loss and blood transfusion in patients with hip fractures. (Strong recommendation) 11. Interdisciplinary/Multidisciplinary care programs 11.1. On admission, offer patients a formal, acute orthogeriatric or orthopaedic ward-based fracture program that includes the following steps (Conditional recommendation): 11.1.1. Comprehensive orthogeriatric assessment to evaluate both current and baseline level of functioning 11.1.2. Rapid optimization to make patient fit for surgery 11.1.3. Identify individual goals for multidisciplinary rehabilitation to recover mobility and independence, and to achieve return to pre-fracture residence when possible 11.1.4. Offer longitudinal, coordinated, orthogeriatric and multidisciplinary review 11.1.5. Provide liaison or integration with related services, particularly mental health (delirium prevention), falls prevention, bone health, primary care and social services 11.1.6. Clinical and service governance responsibility for all stages of the pathway of care and rehabilitation, including those provided in the community. 12. Postoperative rehabilitation 12.1. In patients undergoing surgical stabilization of hip fractures, early mobilization, including functional movement within 24–48 hours postoperatively is recommended, provided the patient is medically and mobilization is consistent with the surgeon’s postoperative instructions (Strong recommendation) 12.2. Following hip fracture surgery, weight-bearing should be initiated as early as clinically feasible, with full weight-bearing as tolerated recommended after stable fixation, unless contraindicated by surgical or patient-specific factors (Conditional recommendation) 12.3. Rehabilitation after hip fracture surgery should follow a structured, phased pathway, spanning the acute inpatient phase, home or inpatient rehabilitation services, and outpatient rehabilitation, aligned with the patient’s recovery stage and care setting (Conditional recommendation) 12.4. Fall prevention strategies should begin with identification and management of underlying fall risk factors, including muscle weakness, balance deficits, cognitive impairment, medication-related side effects, orthostatic hypotension, visual impairment, and environmental hazards. These strategies should be systematically integrated into all phases of postoperative rehabilitation following hip fracture surgery (Conditional recommendation). 12.5. Standardized functional and mobility outcome measures, such as the Timed Up and Go Test (TUG test), should be used regularly to guide rehabilitation progression and monitor recovery after hip fracture surgery. (Conditional recommendation) 12.6. Discharge planning should begin early during hospitalization and be individualized based on medical stability, functional recovery, cognitive status, family support, and access to rehabilitation services. In the Egyptian healthcare setting, most patients require a short inpatient stay followed by home-based or facility-based rehabilitation. Early discharge within 24–48 hours may be considered for selected, medically stable patients with adequate family support and rehabilitation access. Same-day or next-day discharge should be limited to exceptional cases. (Conditional recommendation) 12.7. Following hip fracture surgery, appropriate assistive devices should be prescribed and regularly reassessed to support safe ambulation. A walker is recommended in the early postoperative phase, with progression to a cane held in the contralateral hand to the operated limb as balance, strength, and weight-bearing tolerance improve. (Good practice statement) 13. Patient and carer information 13.1. It is crucial to offer the patients (or when appropriate, their carers) information about their medical diagnosis and its implications and treatment options and management plan either verbally or in printed form (Good practice statement) |
- Recommendations
Imaging options in occult hip fracture
Recommendation:
1. In adults with clinical suspicion of hip fracture but adequate quality negative standard X-rays (anteroposterior pelvis and lateral hip), cross-sectional imaging should be performed. Specifically:
1.1. Magnetic resonance imaging (MRI) is the preferred modality due to higher diagnostic sensitivity and specificity for occult hip fractures. (Strong recommendation, Moderate quality evidence)
1.2. Computed tomography (CT) should be considered when MRI is unavailable within 24 hours, contraindicated, or impractical. (Conditional Recommendation, Moderate quality evidence)
1.3. If CT is used first and is negative despite ongoing clinical suspicion, MRI should subsequently be obtained to rule out occult fracture (unless contraindicated). (Strong Recommendation, Moderate quality evidence)
Remarks
When to Offer MRI
Clinical scenarios warranting MRI:
- Persistent hip pain, inability to bear weight, or other clinical signs strongly suggestive of proximal femur fracture despite negative X-rays.
- Patients with risk factors: older age, osteoporosis, history of a fall, severe localized pain, or inability to ambulate.
- Cases where precise delineation of fracture pattern and soft tissue injury may affect management.
Rationale:
- MRI detects bone marrow oedema and subtle fracture lines that are otherwise occult on both X-ray and CT. It also identifies associated injuries (e.g., pelvic fractures).
When to Offer CT
Appropriate scenarios:
- MRI is not immediately available (e.g., within 24 hours) due to logistical or capacity limitations.
- Patients with MRI contraindications (pacemakers or other non-MRI compatible implants, severe claustrophobia that cannot be managed).
- Emergently when rapid imaging is needed and immediate MRI would be delayed.
Role of CT:
- CT is more widely available in emergency settings and provides quick evaluation.
- If CT identifies a fracture, treatment can proceed without delay.
- If CT is negative but clinical suspicion persists, patients should proceed to MRI for definitive exclusion.
Summary of evidence
Meta-Analysis and Systematic Evidence
- A recent systematic review and meta-analysis (2024) found that both MRI and CT have good diagnostic efficacy in detecting occult hip fractures. However, MRI consistently showed higher sensitivity and specificity than CT, indicating superior diagnostic accuracy.9
Observational Comparisons
- Retrospective comparative studies indicate that:
- MRI more reliably identifies occult fractures that are not visible on CT.10
- A negative CT cannot fully exclude a hip fracture if clinical suspicion remains high.11
- In some cohorts, CT and MRI detected similar numbers of fractures, but when CT was negative and clinical suspicion persisted, MRI subsequently identified fractures missed by CT.12
Table 2: Diagnostic Accuracy of MRI versus CT for Occult Hip Fracture 9
|
Parameter |
MRI |
CT |
|
Pooled Sensitivity (Meta-analysis) |
0.94 (95% CI: 0.80–0.99) |
0.92 (95% CI: 0.81–0.96) |
|
Pooled Specificity (Meta-analysis) |
0.98 (95% CI: 0.94–1.00) |
0.94 (95% CI: 0.87–0.97) |
|
Positive LR |
8.14 (95% CI: 5.70–108.04) |
7.60 (95% CI: 5.07–34.44) |
|
Negative LR |
0.06 (95% CI: 0.01–0.22) |
0.09 (95% CI: 0.04–0.21) |
|
Area Under the ROC |
~0.99 (excellent) |
~0.98 (excellent) |
|
Summary |
High diagnostic accuracy; slightly superior to CT overall |
Very good accuracy but slightly lower than MRI |
Table 3: GRADE Assessment – Diagnostic Accuracy 9
|
Outcome |
MRI |
CT |
|
Overall Quality of Evidence |
Moderate – multiple studies with QUADAS-2 assessment; consistency in pooled diagnostic performance. |
Moderate (lower than MRI) – similar meta-analytic data but a trend toward slightly lower sensitivity; some studies highlight false negatives. |
|
Risk of Bias |
Generally low in meta-analysis; QUADAS-2 showed minimal concerns. |
Similar quality in QUADAS-2, but clinical follow-up in some cohorts showed missed fractures. |
|
Indirectness |
Directly applicable to patients with suspected occult hip fracture after negative radiographs. |
Same applicability. |
|
Imprecision |
Moderate (CI ranges reflect some uncertainty). |
Moderate (similar CI uncertainty). |
|
Publication Bias |
Not statistically significant in meta-analyses. |
Not statistically significant. |
Rationale for the recommendation
- Patient safety: Untreated occult hip fractures can displace, leading to worse outcomes (pain, morbidity, prolonged immobility).
- Availability: Many centres cannot access urgent MRI; CT may be used practically.
- Contraindications: Standard MRI contraindications (e.g., ferromagnetic implants) increase the importance of CT as an alternative.
- Radiation: CT carries ionizing radiation risk, which should be balanced against clinical urgency.
- MRI: Highest diagnostic accuracy, no radiation exposure, sensitive to marrow oedema, consistent results across studies.
- CT: High specificity but lower sensitivity; potential for false negatives.
Preoperative traction
Recommendation
We advise against the routine use of preoperative traction for patients with a hip fracture. (Conditional recommendation, High quality evidence)
Remarks
Complications, comfort, and pain are important outcomes related to hip fracture. Not using preoperative traction ease the patient’s comfort in bed, decreases pain and lowers the incidence of possible bedridden complications.
Summary of evidence
Overall, there were two high quality13,14 and six moderate studies15-20 addressing preoperative traction. Since 2012, one high13 and one moderate quality study19 investigated preoperative traction. Tosun19 (2018) found that a position splint resulted in significant difference in immobilization comfort score (30.1/100) and pain compared to traction, whereas Endo13 found no differences in pain. Tosun also found that preoperative traction resulted in more pre-operative complications (constipation, pressure ulcers, adhesive plaster allergy, urinary tract infections, pulmonary complications, bleeding in the fractured joint) than a position splint applied for 1 day preoperatively, whereas Endo found no significant differences in complications between traction and no traction. These results are consistent with prior evidence and strengthen the body of evidence indicating that there are no benefits of preoperative traction. The recommendation reflects that there are some instances in which traction may be required (e.g., specific cases with peri-trochanteric fractures), however, in most cases pre- operative traction should not be used.
Rationale for the recommendation
There are no known harms of implementing this recommendation. Use of alternatives to preoperative traction appeared to be acceptable to patients like positioning with pillows.
Timing of surgery
Recommendation
Perform hip fracture surgery on the day of, or the day after admission to hospital (within 48 hours); taking into consideration the patient optimization for surgery. (Conditional recommendation, Moderate quality evidence)
Remarks
Traditionally, hip fracture patients have not always been considered a priority group in accessing theatres and the injury itself is rarely life threatening. However, older people with a hip fracture frequently have multiple co-morbidities, limited physiological reserve and are prone to an increase in complications from prolonged bed rest. Hospitals must therefore be organised in such a way that facilitates timely and planned surgery without delays, meaning not only adequate theatre capacity for trauma surgery and availability of anaesthetists and surgeons, but also a means of rapidly assessing and optimising frail, elderly patients with multiple co-morbidities.
Summary of evidence
Systematic reviews suggested that delay past 48hr increased one-year mortality by 32%. Recent studies, however, have suggested mortality reductions by reducing time to theatre to 24hr and even 12hr from admission21-24
Rationale for the recommendation
Moderate evidence supports that hip fracture surgery within 48 hours of admission is
associated with better outcomes, less hospital stay and is more cost effective. Taking into consideration resource availability, the panel decided to downgrade the recommendation from strong to conditional, provided that reasons for any delay are clearly documented in the patients notes.
Antithrombotic Management
1. Confirm
antithrombotic status early
Recommendation:
On admission, confirm the antithrombotic agent(s), last dose time, renal function and indication (VTE prophylaxis vs therapeutic anticoagulation) before committing to neuraxial or deep regional techniques. (Strong recommendation, Low quality evidence)
Remarks
Document last known dose time from a reliable source (medication list, family, pharmacy, or electronic record). If timing is uncertain, manage as 'dose within the minimum interruption interval'.
Summary of evidence
The strong recommendation is based on low-certainty evidence derived from international consensus guidelines, primarily the American Society of Regional Anesthesia and Pain Medicine (ASRA) Fifth Edition Guidelines25 and the Joint ESAIC/ESRA Guideline26. These guidelines emphasize that the cornerstone of safe regional anesthesia in anticoagulated patients is an accurate, timely medication history. The evidence supporting this is largely indirect, stemming from case series and root-cause analyses of catastrophic complications like spinal hematoma, where a common contributing factor was inadequate documentation or verification of anticoagulant timing. The guidelines explicitly state that agent-specific interruption intervals cannot be applied safely without knowing the exact drug, dose, last administration time, and renal function (critical for DOAC and LMWH clearance). This operational step is considered a fundamental patient safety requirement in all perioperative pathways.
Rationale for the recommendation
Timely, accurate drug history avoids unnecessary delays and reduces the risk of neuraxial or deep block hematoma from inadvertently performing a procedure within an unsafe interval.
2.VTE prophylaxis when surgery is delayed:
Recommendation:
If surgery is delayed beyond the day of admission, consider pharmacological VTE prophylaxis if VTE risk outweighs bleeding risk. Ensure the last dose is at least 12 hours before surgery for low dose LMWH and at least 24 hours for high dose LMWH and fondaparinux. (Strong recommendation, Moderate quality evidence)
Remarks
Continue mechanical prophylaxis when pharmacological prophylaxis is withheld. Reassess daily as renal function and bleeding risk evolve.
Summary of evidence
This strong recommendation is supported by moderate-certainty evidence from7,27 on VTE prevention. NICE recommends that patients with hip fractures should receive pharmacological VTE prophylaxis if surgery is delayed beyond the day of admission. The specified minimum intervals (12 hours for prophylactic LMWH, 24 hours for therapeutic LMWH/fondaparinux) are based on pharmacodynamic studies of anti-Xa activity and its correlation with bleeding risk. The evidence balancing VTE risk against bleeding risk comes from large orthopaedic trials and meta-analyses, which show that while hip fracture patients have a very high baseline VTE risk, indiscriminate pre-operative dosing increases the hazard of surgical and neuraxial bleeding. The "delay-triggered" approach is a pragmatic synthesis of this evidence, aiming to protect patients from VTE during unavoidable waits without compromising the option for regional anaesthesia or increasing intraoperative bleeding.
Rationale for the recommendation
Hip fracture patients are at high VTE risk; however, unnecessary pre-operative dosing can force neuraxial/deep procedures to be deferred. A 'delay-triggered' approach balances both risks.
3. Choose regional technique based on compressibility (deep vs superficial)
Recommendation:
Treat deep (non-compressible) nerve blocks like lumbar plexus or paravertebral blocks, the same way as neuraxial blocks in respect to VTE prophylaxis drugs interruption timing. For superficial (compressible) single-shot blocks like femoral nerve or fascia iliaca plane blocks, apply a site-based bleeding risk assessment and proceed when the expected benefit outweighs bleeding risk. (Strong recommendation, Low quality evidence)
Remarks
If neuraxial timing criteria are not met, general anaesthesia with a superficial compressible block is a common compromise to preserve analgesic benefit while avoiding deep needle placement.
Summary of evidence
The strong recommendation for this risk-stratified framework is based on low-certainty evidence from expert consensus, primarily outlined in the Joint ESAIC/ESRA Guideline26. This guideline introduces a key conceptual shift: not all regional techniques carry the same bleeding risk. The evidence underpinning this distinction is anatomical and pathophysiological. Deep, non-compressible sites (e.g., neuraxial space, deep plexus) pose a risk of concealed, expanding hematoma with potential for permanent neurological injury, as documented in case reports. In contrast, bleeding at superficial, compressible sites (e.g., fascia iliaca plane) is theoretically easier to detect and control with external pressure. While high-quality comparative studies are lacking, the framework is considered a rational approach to maximize the benefits of regional analgesia (supported by the Cochrane review by Guay et al., 2020)28 while mitigating the most severe risks in patients on antithrombotics.
Rationale for the recommendation
Nerve blocks are generally categorized as superficial or deep based on anatomical location and tissue compressibility. Superficial nerve blocks target nerves in relatively accessible areas surrounded by compressible tissue. Examples include femoral, interscalene, and axillary blocks etc. These blocks are easier to visualize with ultrasound and pose a lower risk of serious bleeding. Deep nerve blocks, such as lumbar plexus or paravertebral blocks, involve deeper, non-compressible tissue. Compressible sites permit rapid detection and management of bleeding complications; deep sites do not. This supports a risk-stratified approach rather than a one-size-fits-all prohibition.
4. Minimum interruption intervals before neuraxial or deep procedures (summary)
Recommendation:
Use Annex 2: Minimum interruption intervals (summary table) for a consolidated table. Key principles 17,18:
· Dose intensity and renal function matter for LMWH and DOACs; insertion and removal of neuraxial catheters are both timing events (Strong recommendation, High quality evidence)
· It is advised to check platelet count if LMWH has been used for more than 4 days due to heparin-induced thrombocytopenia risk. (Conditional recommendation, Low quality evidence)
5. Operational rules for LMWH and neuraxial/deep catheters
Recommendation:
When neuraxial or deep catheters are used, coordinate LMWH dosing with both catheter placement and removal.
· Stop low-dose LMWH at least 12 hours before placement or removal of the catheter, and for 24 hours before placement or removal in case of high dose LMWH.
· In all cases; (low and high dose LMWH); start first LMWH dose at least 12 hours after placement and at least 4 hours after removal.
(Strong recommendation, Moderate quality evidence)
Remarks
If LMWH has been administered for more than 4 days, check platelet count before neuraxial/deep block or catheter removal. Use 1.5 or less for 'acceptable INR' where vitamin K antagonists are involved. 29
Summary of evidence
These strong recommendations are supported by moderate-certainty evidence synthesizing pharmacodynamic data and large-scale observational safety registries. The specific time intervals for each drug class (LMWH, DOACs, fondaparinux, etc.) before neuraxial/deep blocks are meticulously detailed in the ASRA (2025)25 and ESAIC/ESRA (2022)26 guidelines. These intervals are derived from studies of the drug's half-life, time to maximum effect, and time for return of haemostatic function, often modified by renal function for renally cleared agents. The evidence for the critical importance of coordinating catheter removal with anticoagulant dosing is particularly strong, stemming from analysis of case reports of spinal hematoma, which identified catheter removal as a high-risk event. The operational rules for LMWH (e.g., 12-hour windows for once-daily dosing) are based on sustained clinical experience and pharmacodynamic modelling that aims to avoid peak anticoagulant activity during needle placement or catheter manipulation, thereby reducing the risk of this rare but devastating complication.
Rationale for the recommendation
Catheter placement and removal create tissue planes susceptible to bleeding. Timing anticoagulant exposure around these events reduces catastrophic but rare complications.
6.Post-operative prophylaxis duration and agent selection
Recommendation:
Provide post-operative VTE prophylaxis according to individual risk assessment; extended prophylaxis (e.g., 28–35 days) is commonly used after hip fracture surgery. (Conditional recommendation, Moderate quality evidence)
Remarks
Choice of agent (LMWH, DOAC, warfarin, or aspirin in selected patients) should reflect surgical plan, renal function, bleeding risk, and contraindications, and must be coordinated with any neuraxial/deep catheter use.
Summary of evidence
This conditional recommendation is based on low-to-moderate certainty evidence from various orthopaedic and thromboprophylaxis guidelines, including NICE NG89, AAOS (2021), and PROSPECT (2024)2,27,30. The evidence consistently identifies hip fracture surgery as a highest-risk scenario for VTE, justifying pharmacologic prophylaxis. Randomized controlled trials and meta-analyses provide moderate-certainty evidence that extended prophylaxis (e.g., 28-35 days) reduces the risk of symptomatic VTE compared to shorter (e.g., 10-14 day) regimens. However, the evidence is less clear on the net benefit, as extended therapy increases the risk of major bleeding. This trade-off leads to the conditional strength of the recommendation, necessitating individualization based on patient-specific bleeding risk, mobility, and renal function. The guidance to coordinate agent choice with neuraxial catheters is again directly informed by the ASRA/ESAIC/ESRA guidelines to prevent catheter-related hematoma.
Rationale for the recommendation
The VTE risk remains elevated after discharge. Extended prophylaxis may reduce symptomatic VTE at the cost of increased bleeding in some subgroups; thus, individualization is required.
Perioperative Analgesia
1. Structured
pain assessment and reassessment:
Recommendation
Assess pain score immediately on presentation (at rest and on movement) and reassess within 30 minutes after any analgesic intervention; then hourly until pain is controlled, and thereafter with routine observations. (Strong recommendation, Moderate quality evidence)
· In conscious patients use the Numerical Pain Rating (NPR) score to measure pain
· In case of cognitive impairment, use observational tools (e.g., FLACC [Face, Legs, Activity, Cry, Consolability] scale) and incorporate caregiver input.
· Always document sedation score and respiratory rate after opioid escalation
Remarks
In conscious patients use the Numerical Pain Rating (NPR) score to measure pain and in case of cognitive impairment, use observational tools (e.g., FLACC [Face, Legs, Activity, Cry, Consolability] scale)31 (Annex 3: FLACC score and Ramsay sedation score), and incorporate caregiver input. Always document sedation score32 and respiratory rate after opioid escalation.
Summary of evidence
This recommendation is strongly supported by moderate-certainty evidence from the NICE CG124 (2025 update)7 hip fracture management guideline. The guideline explicitly mandates structured pain assessment at presentation and after each analgesic intervention. The evidence for using observational pain scales (e.g., the FLACC scale)31 in patients with cognitive impairment or delirium is drawn from validation studies in geriatric and postoperative populations, which show improved detection of pain compared to self-report alone. Regular reassessment protocols are linked in observational studies to more timely analgesia adjustments, reduced incidence of severe pain during movement or positioning, and a lower risk of opioid-related oversedation. This approach is foundational to the "delirium-aware" care emphasized in multidisciplinary hip fracture pathways.
Rationale for the recommendation
Early pain control enables imaging, nursing care, and positioning for anaesthesia, and reduces delirium risk. Reassessment prevents both undertreatment and oversedation.
2. Baseline analgesia: regular paracetamol (acetaminophen):
Recommendation
Offer regular paracetamol/acetaminophen every 6 hours pre- and post-operatively unless contraindicated; use intravenous dosing when oral administration is unreliable. (Strong Recommendation, Moderate quality evidence)
Remarks
Review maximum daily dose in low body weight, frailty, or liver disease; include all sources (drug combination tablets) of acetaminophen to avoid unintentional overdose.
Summary of evidence
The strong recommendation is based on moderate-certainty evidence from NICE CG1247, which identifies regular scheduled paracetamol as the first-line analgesic for hip fracture patients. The evidence synthesizes data showing that paracetamol provides effective baseline analgesia with a superior safety profile compared to NSAIDs or opioids in older adults, particularly regarding gastrointestinal, renal, and bleeding risks. The emphasis on intravenous administration when the oral route is unreliable is supported by pharmacokinetic studies in frail or acutely ill older adults demonstrating more predictable bioavailability. The caution regarding maximum daily dose (especially with combination products) is a direct application of pharmacovigilance data on acetaminophen-induced hepatotoxicity, which is cited in drug safety communications from regulatory bodies like the FDA and MHRA.
Rationale for the recommendation
Paracetamol provides baseline analgesia with a favorable safety profile compared with opioids in older adults when dose limits are respected.
3. Opioid rescue: small, titrated immediate-release dosing:
Recommendation
Use opioids as rescue therapy with small, titrated doses (prefer immediate-release oral or carefully titrated IV boluses) when paracetamol alone is insufficient. Avoid initiating prolonged-release opioids in the acute perioperative phase. (Strong recommendation, Moderate quality evidence)
Remarks
Start low and titrate slowly, especially in renal impairment and cognitive impairment. Implement routine bowel regimen and antiemetic when opioids are used.
Summary of evidence
This strong recommendation is grounded in moderate-certainty evidence primarily from NICE CG1247 and reinforced by geriatric pharmacology principles. NICE recommends immediate-release opioids as rescue therapy when paracetamol is insufficient. The evidence against initiating long-acting opioids in the acute phase comes from cohort studies and expert consensus (e.g., Association of Anaesthetists guideline)33, which associate these agents with a higher risk of sedation, respiratory depression, and delirium in opioid-naïve older patients. The "start low, go slow" titration approach is supported by pharmacokinetic data showing increased sensitivity and variable clearance in older adults, especially with renal impairment (notably for morphine metabolites). The mandatory co-prescription of a bowel regimen is based on high-quality evidence demonstrating the near-universality of opioid-induced constipation and its negative impact on recovery.
Rationale for the recommendation
Immediate-release dosing allows rapid titration to effect and reduces risk of accumulation and oversedation.
4. Early regional analgesia (single-shot block) where available:
Recommendation
Offer an early peripheral nerve block [e.g., fascia iliaca, femoral, or Pericapsular Nerve Group (PENG)] block when trained staff and ultrasound are available, to improve pain control and reduce systemic opioid requirements. Do not delay surgery for block placement. (Conditional recommendation, Moderate quality evidence)
Remarks
Coordinate with antithrombotic status using the deep vs superficial framework; monitor for local anaesthetic systemic toxicity and document motor block/falls risk.
Summary of evidence
The conditional recommendation is supported by moderate-certainty evidence from two key sources. First, NICE CG1247 recommends considering a nerve block if pain is severe or to limit opioid dose. More robust, procedure-specific evidence comes from the Cochrane systematic review by Guay et al. (2020)28, which analyzed randomized trials of peripheral nerve blocks for hip fracture. This review concluded that blocks (especially fascia iliaca compartment blocks) provide superior pain relief on movement, reduce systemic opioid consumption, and are associated with a lower risk of postoperative confusion (delirium). The recommendation not to delay surgery for a block is a pragmatic one, based on pathway analyses from NICE that prioritize timely surgery. Coordination with antithrombotic therapy is meticulously detailed in the ASRA (Kopp et al., 2025)25 and ESAIC/ESRA (Kietaibl et al., 2022)26 guidelines, which provide risk-stratified timing for blocks based on anticoagulant type.
Rationale for the recommendation
Blocks facilitate positioning, reduce opioid exposure, and may improve early rehabilitation participation.
5. Supportive measures and monitoring:
Recommendation
When opioids are used, prescribe antiemetic and bowel regimen, monitor sedation score, respiratory rate, and oxygen saturation, and screen for delirium daily. Encourage early mobilization and physiotherapy when clinically appropriate. (Strong recommendation, Low quality evidence)
Remarks
Avoid benzodiazepines unless clearly indicated; minimize anticholinergic burden.
Summary of evidence
The strong recommendation is supported by low-certainty direct evidence but is a cornerstone of multidisciplinary hip fracture care pathways like NICE CG1247. The evidence for routine antiemetic and bowel prophylaxis with opioids is extrapolated from high-quality studies in other surgical populations and is considered standard of care to prevent iatrogenic harm. The link between structured monitoring (sedation, respiration, oxygenation) and reduced opioid-related adverse events is supported by patient safety initiatives. The emphasis on daily delirium screening is mandated by NICE and is based on studies showing that systematic detection leads to earlier intervention. The recommendation to avoid benzodiazepines is strongly supported by multiple high-quality studies and meta-analyses (cited in geriatric and delirium guidelines) that consistently associate them with increased delirium risk, falls, and cognitive decline in older hospitalized patients.
Rationale for the recommendation
Complications from opioids (respiratory depression, delirium, constipation) are common drivers of poor outcomes and longer admissions.
6. NSAIDs and COX-2 inhibitors: selective use only:
Recommendation
Avoid routine NSAIDs/COX-2 inhibitors in frail older hip fracture patients. Consider them only when a senior clinician documents a favourable risk-benefit assessment and there are no contraindications (renal dysfunction, high bleeding risk, active GI disease, interacting anticoagulants). (Conditional recommendation, Low quality evidence)
Remarks
This recommendation reflects the tension between sources: NICE CG1247 does not recommend NSAIDs for hip fracture, whereas PROSPECT recommends NSAIDs or COX-2 inhibitors as part of multimodal analgesia when appropriate.
Summary of evidence
This conditional recommendation arises from a tension between guideline sources, leading to low-certainty evidence for routine use. The PROSPECT recommendations (2024)34 list NSAIDs or COX-2 inhibitors as a component of basic multimodal analgesia for hip fracture repair when no contraindications exist, citing evidence for their opioid-sparing and anti-inflammatory effects. However, NICE CG124 explicitly does not recommend NSAIDs for this population due to concerns about renal impairment, gastrointestinal bleeding, and interference with bone healing. This guideline's default "avoid" stance is justified by the high prevalence of these risk factors in the typical frail, older hip fracture population, as documented in large epidemiological studies. The requirement for a senior clinician's documented risk-benefit assessment is a safety mechanism to identify the minority of patients (e.g., robust, with normal renal function) who might benefit from short-term use.
Rationale for the recommendation
A default-to-avoid stance in high-risk patients reduces preventable renal and bleeding complications while allowing clinician discretion for lower-risk individuals.
7. Epidural analgesia: selected cases only:
Recommendation
Routine use of epidural analgesia for hip fracture surgery is discouraged. If used, restrict to selected cases under acute pain service or senior anaesthesia oversight, with explicit anticoagulant coordination and haemodynamic monitoring. (Conditional recommendation, Low quality evidence).
· Our current practice in Egypt still permits the use of epidural anaesthesia / analgesia in selected patients with consideration of the anticoagulants use/withhold recommended duration for catheter insertion and removal, in view of the immaturity of regional blocks training especially in rural areas.
Remarks
Risks include hypotension, motor block with falls risk, urinary retention, infection, and neuraxial hematoma (timing dependent).
Summary of evidence
The strong recommendation against routine use is based on low-certainty, procedure-specific evidence from the PROSPECT Working Group (2024)34. PROSPECT's analysis found limited high-quality studies demonstrating a clear advantage of epidural over systemic or peripheral nerve block techniques for hip fracture surgery, while the risks (hypotension, motor block/falls, urinary retention, infection, and neuraxial hematoma) are well-documented in the broader anaesthesia literature. The guidelines from ASRA25 and ESAIC/ESRA26 heavily inform the strict anticoagulant coordination required. The acknowledgment of potential use in selected cases (e.g., with Acute Pain Service oversight) reflects clinical pragmatism, allowing for its consideration in complex pain scenarios or where regional block expertise is limited, provided the stringent safety protocols for anticoagulant management and hemodynamic monitoring are followed.
Rationale for the recommendation
In this frail population, the risk and monitoring burden often outweigh incremental benefit compared with peripheral blocks and systemic multimodal regimens.
8. Multimodal analgesia: overall strategy and core components:
Recommendation
Use a layered multimodal regimen for all hip fracture patients unless contraindicated: regular paracetamol (acetaminophen) as baseline therapy, early peripheral nerve block (single-shot fascia iliaca or femoral nerve block where available), and opioids for rescue analgesia using small, titrated immediate-release doses. Reserve short-course NSAID/COX-2 inhibitor only in carefully selected low-risk patients (Strong recommendation, Moderate quality evidence)
Remarks
Tailor component selection to frailty, renal function, gastrointestinal/bleeding risk, and cognitive status. Prefer established blocks (FICB/FNB); consider newer techniques (e.g., PENG) only where local expertise exists and within protocols, as procedure-specific evidence remains limited. Avoid routine use of adjuvant techniques/drugs with insufficient procedure-specific evidence (e.g., IV dexmedetomidine/clonidine as analgesic adjuncts, routine local infiltration analgesia) outside specialist pathways. Do not delay surgery to complete the multimodal regimen; reassess pain and sedation after each escalation (Annex 4: Multimodal analgesia for hip fracture).
Summary of evidence
This recommendation is supported by convergent guidelines and systematic review of evidence. A multidisciplinary UK consensus statement endorses multimodal analgesia throughout the peri-operative pathway, defining it as combining analgesics with different mechanisms to improve analgesia and permit lower doses of individual drugs, thereby reducing adverse effects.35 PROSPECT34 procedure-specific guidance for hip fracture repair recommends basic multimodal analgesia with scheduled paracetamol and NSAIDs or COX-2-selective inhibitors when not contraindicated, combined with a single-shot femoral nerve block or fascia iliaca compartment block, and reserving opioids as rescue analgesia. NICE CG1247 similarly positions regular paracetamol as first-line, immediate-release opioids as additional analgesia, and suggests adding nerve blocks when pain control is inadequate or to limit opioid dose. Evidence syntheses (e.g., Cochrane reviews)28 demonstrate that peripheral nerve blocks reduce pain on movement and opioid consumption, with signals for reduced postoperative confusion/delirium, supporting the opioid-sparing rationale of multimodal strategies.30 Direct trials of bundled multimodal pathways in hip fracture are limited; therefore, overall certainty is moderate, driven by consistent benefits across components and strong expert consensus Error! Reference source not found..
Rationale for the recommendation:
A multimodal regimen improves comfort and function (especially pain-on movement), reduces opioid exposure and related harms, and supports timely imaging, regional/spinal positioning, and early rehabilitation.
Anaesthetic management
1.
Do not
delay surgery for non-time-critical optimization:
Recommendation:
Proceed to surgery as soon as feasible once immediately reversible problems are addressed (e.g., hypoxia, hypovolaemia, severe electrolyte derangements, uncontrolled pain). (Strong Recommendation, Moderate quality evidence)
Remarks
Optimization should run in parallel with theatre preparation. Avoid delays for routine investigations unless they change perioperative management (Annex 5: Anaesthetic management pathway (hip fracture surgery)).
Summary of evidence
This recommendation is strongly supported by the NICE CG124 guideline7 and its surveillance updates, which form the cornerstone of standardized hip fracture care pathways in many healthcare systems. These pathways are explicitly designed to expedite surgery once immediately reversible problems are corrected, with the primary outcome of reducing complications associated with prolonged immobility and pain. The evidence, rated as moderate certainty, is drawn from large observational studies and audits of these pathways, which consistently demonstrate that timely surgery (typically within 36 hours) is associated with lower mortality, reduced length of stay, and fewer medical complications like pneumonia and pressure sores. The rationale is that multidisciplinary, parallel processing of optimization and theatre preparation
Rationale for the recommendation
Delays increase pain, immobility-related complications, and delirium risk. Focused optimization improves safety without compromising time-to-theatre.
2. Technique selection: spinal/regional vs general anaesthesia:
Recommendation:
Either neuraxial (spinal) or general anaesthesia is acceptable. Choose the technique that can be delivered safely and promptly given antithrombotic timing, physiological reserve, airway risk, expected surgical duration, and local expertise. (Conditional recommendation, High quality evidence)
Remarks
If neuraxial is contraindicated or not feasible, proceed with general anaesthesia and use a peripheral nerve block when feasible for opioid-sparing.
Summary of evidence
The conditional recommendation for technique choice is primarily informed by high-certainty evidence from the landmark REGAIN trial36, a large pragmatic randomized controlled trial. This study directly compared spinal anaesthesia to general anaesthesia in older adults undergoing hip fracture surgery and found no significant difference in the primary composite outcome of death or an inability to walk at 60 days. Critically, it also found no difference in key secondary outcomes, including the incidence of postoperative delirium. This pivotal evidence overturned the long-held assumption of neuraxial superiority. Consequently, contemporary guidelines from the Association of Anaesthetists33 (2021) and the PROSPECT Working Group (2024)34 explicitly state that neither technique is preferred. The decision should be individualized, factoring in logistical constraints (e.g., timing of last antithrombotic dose as per ASRA25/ESAIC26 guidelines) and patient physiology to avoid delays and ensure hemodynamic stability.
Rationale for the recommendation
Clinical heterogeneity is substantial (frailty, respiratory disease, antithrombotics). A pragmatic approach that avoids delay and preserves haemodynamic stability is likely to improve system-level outcomes.
3. Intra-operative physiological targets (common to all techniques):
Recommendation:
Aim to maintain any change in systolic blood pressure/mean arterial pressure within approximately 20% of the patient’s baseline, avoid hypoxia and hypercarbia, maintain normothermia, and use a proactive vasopressor strategy with judicious fluids. (Strong recommendation, Low quality evidence)
Remarks
Consider invasive arterial pressure monitoring for higher-risk patients (e.g., severe aortic stenosis, significant cardiopulmonary disease, anticipated major blood loss).
Summary of evidence
While direct randomized trial evidence is of low certainty, the strong recommendation stems from a synthesis of observational studies and expert consensus detailed in the Association of Anaesthetists guideline (Griffiths et al., 2021)33. This guidance explicitly links intraoperative hypotension and hypoxia to increased risks of acute kidney injury, myocardial injury, and postoperative delirium in this frail population. The specific target of maintaining systolic or mean arterial pressure within 20% of baseline is a widely adopted consensus threshold to define intraoperative hypotension. The call for proactive vasopressor use and judicious fluid management is based on pathophysiological understanding of reduced autonomic reserve in older adults. The guideline emphasizes that standardized monitoring and treatment protocols improve team coordination and reduce outcome variability, even in the absence of definitive RCTs.
Rationale for the recommendation
Older hip fracture patients have limited physiological reserve. Standardized targets improve team coordination and reduce unwarranted variation
4. Cemented hemiarthroplasty and bone cement implantation syndrome (BCIS):
Recommendation:
For cemented arthroplasty, identify high-risk patients and apply BCIS (Bone Cement Implantation Syndrome) precautions: a team 'cement pause', maintain blood pressure close to baseline, optimize oxygenation, and have vasopressors immediately available. (Strong Recommendation, Moderate quality evidence:)
Remarks
Escalate monitoring for high-risk patients and ensure explicit communication with surgeons during femoral canal preparation and cement insertion.
Summary of evidence
The strong recommendation and moderate-certainty evidence are derived from dedicated safety analyses, most notably the Association of Anaesthetists safety guideline (2015)30 on reducing risk from cemented hemiarthroplasty. This guideline systematically reviews case series and cohort studies documenting BCIS, characterized by hypoxia, hypotension, pulmonary hypertension, and/or cardiac arrest during cement implantation. The evidence underpinning the "cement pause" and preparedness strategy is based on root-cause analyses of adverse events, which identify communication failure and lack of readiness as contributory factors. The recommended bundle of maintaining blood pressure, optimizing oxygenation, and having vasopressors drawn up is a pragmatic response to the time-critical nature of BCIS, aimed at improving rescue success, as supported by subsequent adoption in international guidelines like those from the American Academy of Orthopaedic Surgeons (AAOS, 2021)37.
Rationale for the recommendation
BCIS events are time-critical; preparedness and coordinated action reduce severity and improve rescue success.
5. Immediate post-operative priorities:
Recommendation:
Implement multimodal analgesia, delirium prevention measures (adequate pain control, oxygenation, hydration, sleep-wake support), and early mobilization. Coordinate VTE prophylaxis timing with any neuraxial or deep catheter use. (Strong recommendation, Moderate quality evidence)
Remarks
Communicate a clear post-operative plan to ward/HDU: analgesia regimen, delirium risk mitigation, respiratory support needs, and anticoagulant timing.
Summary of evidence
This strong recommendation is supported by moderate-certainty evidence synthesizing multiple guideline sources. The core principle of multimodal, opioid-sparing analgesia is strongly evidenced by the Cochrane review by Guay et al. (2020)28, which confirms that peripheral nerve blocks provide superior pain relief and reduce opioid-related side effects. Delirium prevention is a central pillar of the NICE CG1247 pathway, which links adequate pain control, oxygenation, and early mobilization to reduced delirium incidence. The critical need to coordinate neuraxial or deep catheter management with pharmacologic VTE prophylaxis is exhaustively detailed in the Fifth Edition ASRA Guidelines (Kopp et al., 2025)25 and the joint ESAIC/ESRA guideline (Kietaibl et al., 2022)26, which provide evidence-based minimum neuraxial block intervals for various antithrombotic agents. Finally, the PROSPECT recommendations34 provide procedure-specific endorsement for a structured postoperative bundle combining these elements to facilitate early rehabilitation and improve recovery trajectories.
Rationale for the recommendation
The immediate postoperative phase is when delirium, respiratory compromise, and immobility complications often emerge; structured bundles reduce risk.
Planning the theatre team
Recommendation
· Schedule hip fracture surgery on a planned trauma list
· Consultants or senior staff must supervise trainees and junior members of the anaesthesia, surgical, and theatre teams when they carry out hip fracture procedures (Good practice statement)
Remarks
Hip fracture patients should be prepared for the next operative list after admission, with a senior orthopaedic surgeon and an anaesthetist attending the surgery. The presence of a dedicated team for the management of geriatric hip trauma patients is recommended.
Summary of evidence
Planning the theatre team for the management of geriatric hip trauma patients is recommended7. A comprehensive geriatric fracture program has been described38,39 as an alternative approach to managing fragility fractures. An organized geriatric hip fracture program provides numerous benefits to patients with hip fractures, care providers, and health systems. Protocol-driven perioperative approaches should be employed, focusing on pre, intraoperative, and postoperative optimization of the patient to facilitate early repair of the fracture that may then translate into better outcomes and hence alleviate the individual patient's burden as well as the socioeconomic load for society. These benefits include shorter time to surgery, earlier postoperative mobilization, shorter hospital stay, reduced in-hospital mortality, and reduced postoperative complications.
Rationale for the recommendation
People with a hip fracture can experience pain and anxiety while waiting for an operation. Delays in surgery are associated with negative outcomes for mortality and return to mobility. This approach aims to reduce unnecessary delays, which are associated with negative outcomes and prolonged hospital stays for the patient. It also helps to avoid repeated fasting and potential cancellations often associated with emergency lists. A planned trauma list includes specific healthcare professionals with the expertise required for hip surgery. Senior staff supervision can help to reduce the risk of complications during the surgery. Senior supervision is a crucial factor for patients, who rate the presence of specialists as the most important factor in their preference for a planned operation, as it can reduce the risk of complications during surgery.
Stable Femoral Neck Fractures
Recommendation
In patients with stable femoral neck fractures (impacted/non-displaced, Garden’s I and II, Annex 6: Garden Classification of Femoral Neck Fracture), internal fixation or arthroplasty may be considered, after assessment of the patient and imaging of the hip joint. (Conditional recommendation, Low quality evidence)
Remarks
The decision of management of undisplaced apparently stable femoral neck fractures is multifaceted and depends on several factors (Annex 6: Garden Classification of Femoral Neck Fracture). The bone quality and the sagittal tilt seen in the lateral view or CT scan affect the decision-making of internal fixation vs arthroplasty. The pre-injury functional state of the patient also affects the decision.
Summary of evidence
The decision-making of internal fixation in undisplaced femoral neck fracture is conditioned on the true stability of the fracture, Garden classifications I and II without posterior or anterior tilt 40, 41 and the relatively good bone quality for the anchor of the internal fixation tools. There is no reported superior long-term outcome of arthroplasty compared to internal fixation 42, 2, 7.
Rationale for the recommendation
Internal fixation may be the preferred treatment for physiologically fit elderly patients with Garden I and II, with posterior tilt <20°, good bone quality, independent ambulation, and reasonable life expectancy. Primary arthroplasty should be considered when the probability of fixation failure is high. It is indicated when posterior tilt >20° (Okike K et al. 2019, Papadelis E et al. 2023), associated severe osteoporosis, frailty, and poor compliance of the patient, and pre-existing hip osteoarthritis. Age >80 years with multiple risk factors is also an indication. Arthroplasty did not show superior long-term outcomes compared to internal fixation of non-displaced femoral neck fractures.
Unstable femoral neck fractures – arthroplasty vs fixation
Recommendation:
For displaced (Garden III/IV) fractures neck femur in ambulatory or functionally independent elderly patient, HA or THA is strongly recommended over internal fixation. (Strong Recommendation, High quality evidence:).
Remarks
Fixation is associated with high failure rates (25–40%), frequent reoperations, and inferior functional outcomes. Compared with the internal fixation group, patients that underwent hemiarthroplasty had a lower reoperation rate and an equivalent overall mortality rate 7,37,43-45
Contraindications to arthroplasty:
1. Patient was non ambulatory pre fracture (bedbound or wheelchair- dependent)
2. Life expectancy is less than 12 months (metastatic cancer, end stage organ failure)
3. High surgical risk (ASA IV, not optimized despite best efforts)
Conclusions
In ambulatory patient with unstable fractures femoral neck, Arthroplasty is recommended over fixation
Summary of evidence
Arthroplasty is preferred when:
1. Patient is active and can benefit from better functional outcomes
2. Minimizing reoperation risk is a priority
3. Patient needs faster return to walking with less pain
Internal Fixation may be considered when:
1. Patient has low activity levels or advanced dementia
2. Patient has limited life expectancy
3. High surgical risk Favors shorter procedure time
Important Notes:
1. Mortality rate is similar in both groups (~25% at 1 year)
2. Decision should focus on expected quality of life rather than survival alone
3. Shared decision-making with patient/family is essential after explaining risks and benefits
Rationale for the recommendation
1. Reoperation Rate 46
· Internal Fixation: Very high (26–32%)
· Arthroplasty: Low (6–9%)
· Relative Risk: 0.29 (Favors arthroplasty)
o This means the risk of reoperation is 3.4 times higher with internal fixation
2. Non-union/Avascular Necrosis (AVN)
· Internal Fixation: Common problem (20–40%)
· Arthroplasty: Very rare (<2%)
· Not applicable for relative risk calculation (too rare with arthroplasty)
3. 1-Year Mortality Rate
· Identical in both groups (~25%)
· No statistically significant difference
4. 1-Year Functional Outcomes
· Internal Fixation: Worse mobility, more pain
· Arthroplasty: Better walking ability, less pain
· Standardized mean difference: +0.4 (Favors arthroplasty)
Unipolar/bipolar hemiarthroplasty
Recommendation
Use a femoral stem design other than Austin Moore or Thompson stems for arthroplasties. Unipolar (Austin Moore or Thompson) prosthesis should be used in strictly limited conditions, e. g. Unavailable bipolar prosthesis. (Good practice statement, Moderate quality evidence:)
Remarks
Where the unipolar head has a single articulation between the prosthesis and the acetabulum, the bipolar head offers a second articulation between an inner smaller head and the polyethylene liner of the larger outer head. In theory this reduces stress on the acetabular surface and thereby acetabular erosion. Acetabular erosion is believed to cause pain and impaired hip function.
Summary of evidence
RCTs comparing unipolar and bipolar, showed better Health-related quality of life and hip function for bipolar. The average four years follow-up showed less acetabular erosion by using bipolar47-53.
Rationale for the recommendation
In spite that both replace the femoral head for hip fractures, but bipolar's dual articulation aims for better preservation of the natural socket (acetabulum), and for a better range of motion
UNSTABLE FEMORAL NECK FRACTURES - Total Arthroplasty vs Hemi Arthroplasty
Recommendation
Recommendation 1: For fit, active elderly patients (≥60 years) with displaced femoral neck fractures, Total Hip Arthroplasty (THA) is suggested rather than Hemiarthroplasty (HA) to improve function and reduce revision risk. (Conditional recommendation, Moderate quality evidence)
Recommendation 2: For frail, medically complex, or cognitively impaired patients with limited mobility, Hemiarthroplasty (HA) may be preferred due to shorter operative time and reduced perioperative risk. (Conditional recommendation, Moderate quality evidence)
Recommendation 3: Decisions should incorporate individual patient comorbidities, cognition, pre-fracture mobility, surgical risk, and patient preference. (Strong recommendation, Moderate quality evidence)
Remarks
The pathways below integrate evidence
quality with clinical risk stratification to provide
decision support.
Pathway A: Fit, Active Elderly (>60, Independent, Low Comorbidity)
Goal: Maximize postoperative function and quality of life.
Recommendation:
· Total Hip Arthroplasty (THA) preferred.
Rationale:
- Functional benefit: Moderate evidence supports better function and quality of life with THA44.
- Revision and survivorship: Comparable or lower mid-term revision with THA54.
- Dislocation risk: Slightly elevated but clinically acceptable in active patients55.
Considerations:
- Use THA construct tailored to reduce dislocation risk (dual-mobility etc.)
- Ensure surgical team experience.
Pathway B: Medically Complex, High Surgical Risk (≥60, Multiple Comorbidities, Frailty)
Goal: Minimize perioperative risk and complications.
Recommendation:
· Hemiarthroplasty (HA) preferred.
Rationale:
- Operative time and physiologic stress: HA has shorter operation and less surgical complexity56.
- Functional demands lower: Functional advantage of THA may be less relevant44.
- Dislocation risk lower: HA has lower hip dislocation rates55.
Pathway C: Intermediate Risk (Moderate Comorbidity, Ambulatory but Dependent)
Goal: Balance function and surgical risk.
Recommendation:
· Consider HA if frailty is significant; THA if moderate comorbidity but preserved cognition and activity.
Rationale:
- If cognitive impairment or limited mobility, HA likely sufficient57.
- If moderate risks with good activity, THA may yield functional benefits.
Summary of evidence
The evidence suggests that THA provides slightly better functional outcomes and quality of life than HA, with comparable revision rates and mortality. HA, however, may be preferable in patients with higher surgical risk due to shorter operative time and lower dislocation risk.
A. Functional Outcomes and Quality of Life
|
Outcome |
Evidence Source |
Effect |
Certainty (GRADE) |
Comments |
|
Hip function (Harris Hip Score) |
RCTs + Meta-analyses |
THA modestly higher HHS at 1–5 years |
Moderate |
Meta-analyses show small functional benefit with THA44. |
|
Patient-reported quality of life |
Systematic reviews |
Slightly better with THA |
Moderate |
Data from multiple systematic reviews show improved EQ-5D metrics for THA56. |
|
Early mobility / pain |
RCTs (e.g., NEJM trial) |
Trend favouring THA |
Low-Moderate |
Individual RCTs suggest better early function and pain control with THA58. |
B. Revision and Reoperation
|
Outcome |
Evidence Source |
Effect |
Certainty (GRADE) |
Comments |
|
Revision / Reoperation rates |
Meta-analyses (25 RCTs) |
THA lower or similar |
Moderate |
Some analyses find lower revision with THA; others find no significant difference54. |
|
Mid-term implant survivorship |
RCT/registry analyses |
Comparable |
Moderate |
Registry and trial data suggest similar survivorship up to ~5 years59. |
C. Complications and Risks
|
Outcome |
Evidence Source |
Effect |
Certainty (GRADE) |
Comments |
|
Dislocation |
Observational analyses |
Slightly higher with THA |
Moderate |
Large cohort data show increased dislocation risk with THA (absolute difference small)55. |
|
Operative time |
Meta-analyses |
Longer with THA |
Moderate |
Consistent finding: THA takes longer than HA56. |
|
Mortality |
Meta-analyses |
No clear difference |
Low |
Mortality differences not consistently significant60. |
|
Periprosthetic fracture / infection |
Meta-analyses |
Similar |
Low-Moderate |
Complication trends similar across groups56. |
4. Summary of Evidence
|
Outcome |
Direction of Effect (THA vs HA) |
Magnitude |
Certainty (GRADE) |
Source |
|
Functional outcome (Harris Hip Score) |
THA > HA |
Small–moderate improvement |
Moderate |
RCT meta-analyses (n > 3000) |
|
Health-related quality of life (EQ-5D) |
THA > HA |
Small benefit |
Moderate |
RCT & systematic reviews |
|
Reoperation / Revision |
Similar or lower with THA |
Minimal difference |
Moderate |
RCT + registry |
|
Dislocation |
Higher with THA |
1–2 % absolute increase |
Low–Moderate |
Observational + registry |
|
Operative time |
Longer with THA |
+20–30 min on average |
Moderate |
RCT pooled |
|
Mortality (30–90 days) |
No difference |
Neutral |
Low |
Pooled analyses |
|
Long-term implant survival |
Comparable |
Neutral |
Moderate |
Registry data |
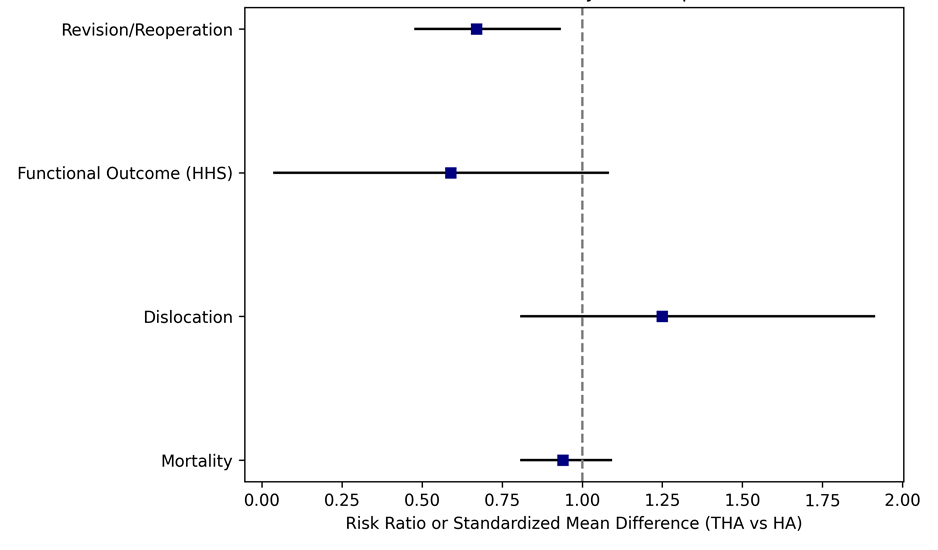
Figure 1: Forest plot summarizing comparative outcomes for THA versus HA across revision rate, functional outcome, dislocation, and mortality
|
Outcome |
No. of Studies (RCTs) |
Participants (n) |
Relative Effect (95% CI) |
Absolute Effect (per 1000) |
Certainty (GRADE) |
|
Revision/Reoperation44,56 |
25 RCTs |
~3,100 |
RR 0.67 (0.48–0.93) |
70 → 47 fewer events |
Moderate |
|
Functional Outcome58,61 |
18 RCTs |
~2,800 |
SMD 0.59 (0.04–1.08) |
+4 HHS points |
Moderate |
|
Dislocation56,58 |
16 RCTs + registries |
>10,000 |
RR 1.25 (0.81–1.91) |
+4 events per 1000 |
Low |
|
Mortality44,56 |
22 RCTs + observational |
>12,000 |
RR 0.94 (0.81–1.09) |
No difference |
Low–Moderate |
Rationale for the recommendation
Fit, Active Elderly Patients Population:
Patients ≥60 years, cognitively intact, ambulatory, independent, with low
surgical risk (ASA I–II).
Recommendation: Perform total hip arthroplasty (THA) rather than hemiarthroplasty to optimize function and quality of life.
Rationale:
- THA provides better functional outcomes and HRQoL.
- Revision rates are comparable or lower long-term.
- Slightly higher dislocation risk can be mitigated by surgical technique (e.g., dual-mobility cup).
Implementation notes:
- Use cemented femoral stems for stability.
- Consider posterior-lateral or anterolateral approaches with soft-tissue repair.
- Employ early mobilization and physiotherapy.
Frail or Medically Complex Patients Population:
Patients ≥75 years, frail, with multiple comorbidities (ASA III–IV), limited ambulation, or cognitive impairment.
Recommendation: Perform hemiarthroplasty (HA) rather than total hip arthroplasty to minimize operative risk.
Rationale:
- Shorter operative time and less blood loss.
- Lower dislocation rate.
- Functional benefit of THA less relevant due to low activity levels.
Implementation notes:
- Use cemented bipolar or unipolar head per institutional preference.
- Prioritize rapid surgery (<48 hours after fracture) and early mobilization.
Intermediate Risk / Mixed Profile Population:
Patients with moderate comorbidities (ASA II–III), ambulatory with aids, or
mildly dependent.
Recommendation: Individualize the choice based on cognitive status, pre-fracture activity, and surgical expertise.
Rationale:
- THA if ambulatory and cognitively intact.
- HA if dependent, low activity, or poor bone quality.
- Engage in shared decision-making with patient and family.
Implementation Considerations
- Institutional expertise: THA requires advanced surgical capability; if not available, HA remains appropriate.
- Cemented fixation: Recommended for both THA and HA in elderly patients.
- Dual mobility cups: Recommended when performing THA in high-dislocation-risk patients.
- Timing: Surgery ideally within 48 hours of fracture to reduce mortality and complications.
- Rehabilitation: Early mobilization and comprehensive geriatric input improve outcomes.
Use of cement in arthroplasty
Recommendation
Cemented stem implants are preferred in patients undergoing surgery with arthroplasty. (Conditional recommendation, High quality evidence)
Remarks
The use of cement in arthroplasty has the potential to secure the implant in an osteoporotic patient and reduce the need for revision secondary to loosening of the prosthesis.
Summary of evidence
Evidence based studies and RCTs showed that cemented fixation in THA after hip fractures is associated with lower revision rates, but similar mortality compared to cementless fixation62-68
Rationale for the recommendation
Some concerns exist around the use of cement and the possibility of bone cement implantation syndrome. Bone cement implantation syndrome is a poorly understood phenomenon which is characterised by one or more of the following: hypoxia, hypotension, cardiac arrhythmias, increased pulmonary vascular resistance and cardiac arrest. It can occur at a number of stages during an arthroplasty including during femoral reaming, insertion of cement or the prosthesis and at the time of reduction of the joint. Its exact aetiology and pathophysiology remain poorly understood as does an accurate figure of the true incidence of the syndrome.
Surgical Approach
Recommendation
In patients undergoing treatment of femoral neck fractures with hip arthroplasty, evidence does not show a favoured surgical approach. Select approach based on surgeon’s experience and preference (Good practice statement)
Remarks
The data in newer studies show no difference in the dislocation rates between the different surgical approaches, including the posterior approach. This contrasts with the earlier data in older publications which showed higher dislocation rate with the posterior approach in comparison to the lateral approach.
Summary of evidence
One high quality study69, seven moderate quality studies70-76 and two low quality studies77,78 were included in the evidence for this recommendation.
The high-quality study75 compared hemiarthroplasty with the anterolateral approach to hemiarthroplasty with the direct lateral approach and reported that while there were elevated levels of serum creatine kinase (CK) observed in the anterolateral approach group, no correlation between CK levels and the Timed Up and Go test or the Trendelenburg sign at 3 months were found.
There were also 8 citations about surgical approach in the surgical treatment of femoral neck fractures with moderate evidence strength. Jianbo (2019)70 reported on a prospective, randomized study of 100 patients. They specifically compared the clinical outcomes and complications of using either the conventional posterior approach, or with using a minimally invasive surgery (MIS) and muscle preserving approach (the Suprapath approach). There was less blood loss, and low transfusion rate in the MIS group. There was less pain, and better function within the first week in the minimally invasive group, but no differences between the groups at the 3-month interval. Repantis (2015)73 reported on the comparative results of a prospective, randomized study in 80 patients using either a MIS approach or in using the posterior approach. It was a single-surgeon series. There was less pain in the MIS group in the short term. There was no difference in any of the other outcomes or complications up to 4 years of follow up. In another comparative study, Saxer (2018)74 reported on the results of 190 patients using either a MIS or using the lateral approach. There was less pain, and faster ambulation in the first 3 weeks in the MIS group. There was no difference in any of the other outcomes, or in the complications between the groups. Verzellotti (2019)76 reported on the comparative results of using the direct anterior (DA) which is muscle preserving, or in using the posterior approach in 100 patients. There was less pain in the DA group in the first month after surgery. There was no difference in the other outcomes or complications between the groups. The operative time was longer in the DA group. Parker (2015)72 reported the comparative results of a multi-centre, prospective, randomized study in 216 patients using either the posterior or the lateral approach. There was no difference in any of the outcome measures analyzed between the groups. In a prospective, randomized study in 150 patients, Ugland (2018)69 reported higher risk of post-surgery Trendelenburg gait when the arthroplasty was done using the lateral approach in contrast to using the anterolateral approach (more abductor muscle preserving). Two low strength articles77,78 (Biber 2012, Skoldenberg 2010) compared the posterior approach to the direct lateral approach for performing arthroplasty in the patients with femoral neck fractures. While neither of the included studies specifically addressed any functional outcomes, they both demonstrated statistically significant differences in dislocation rates, favouring the direct lateral approach.
Rationale for the recommendation
The existing evidence does not support superiority of one surgical approach. Future well designed RCTs should include a comparison of the anterior approach with the posterior and the lateral approach. Any future studies related to surgical approach should also include pain and functional data associated with the approaches. This may have important implications for patient selection and recovery needs such as assistive devices or therapy needs.
Sliding hip screw versus cephalomedullary intramedullary nail for stable intertrochanteric fracture
Recommendation:
In patients with stable intertrochanteric fractures, use of either a sliding hip screw or a cephalomedullary device is recommended. Use a dynamic hip screw (DHS) in preference to an intramedullary nail in patients with stable intertrochanteric fractures (Strong recommendation, High quality evidence)
Remarks
Stable trochanteric fractures are simple two-part intertrochanteric fractures with posteromedial cortical continuity and lateral wall integrity. This fracture pattern is considered stable as it will resist medial compressive loads once reduced.
Summary of evidence
Sliding hip screw versus intramedullary nail for trochanteric fracture
Parker et al. (2012)79 compared the sliding hip screw with the Targon PF intramedullary nail in the treatment of 600 cases of trochanteric hip fracture among 598 patients (mean age=82 years, 80% women). Patients were randomised to treatment with a sliding hip screw or intramedullary nail, and all operations were either performed or supervised by a single orthopaedic surgeon. Patients were reviewed 6 weeks after discharge, and followed up at 3, 6, and 12 months after injury by a research nurse blinded to treatment.
There were no significant differences between groups for total hospital stay (p=0.3), wound healing complications (p=1), other fracture-related complications (p values ranging from 0.12 to 1), loss of hip flexion (p=0.31), or shortening (p=1) at 6 weeks. There were also no significant differences between groups at 1 year for mortality (indicated by Kaplan-Meier curve) or pain (p=0.26). There was, however, a significantly greater recovery of mobility at 1 year with intramedullary nail versus sliding hip screw (difference in mobility score of approximately 0.5 on a scale from 0 to 9, p=0.01).
Cai et al. (2016) 80 in a prospective, randomised blinded study included patients aged over 65 years with stable intertrochanteric fractures (Evans grades I and II). The patients were allocated to one of two groups treated via extramedullary or intramedullary fixation. Extramedullary (compared with intramedullary) fixation of stable intertrochanteric fractures significantly reduces perioperative blood loss but affords similar functional outcomes and times to union. In view of the morbidity and complications associated with acute anaemia and transfusions, extramedullary fixation may be the optimal choice for treatment of stable fractures, being associated with reduced blood loss.
Lewis et al. (2022)81 included randomised controlled trials (RCTs) and quasi-RCTs comparing cephalomedullary nails with extramedullary implants for treating fragility extracapsular hip fractures in older adults. They concluded that Extramedullary devices, most commonly the sliding hip screw, yield very similar functional outcomes to cephalomedullary devices in
the management of extracapsular fragility hip fractures. There is a reduced risk of infection and non-union with cephalomedullary nails; however, there is an increased risk of implant-related fracture that is not attenuated with newer designs.
Sliding hip screw versus proximal femoral locking compression plate for stable intertrochanteric fracture
Zhong B et al. (2014) 82 compared proximal femoral locking compression plate (PFLCP) and DHS fixation in intertrochanteric fractures. They concluded that PFLCP can offer better functional outcomes and fewer complications for subtrochanteric femoral fractures. DHS fixation is preferable for stable intertrochanteric fractures. For unstable intertrochanteric fractures, the value of PFLCP fixation needs to be confirmed by further clinical studies.
Rationale for the recommendation
Stable trochanteric fractures have posteromedial continuity and have lateral wall integrity that enables these fractures to resist compressive medial loads, and if they are well reduced and varus reduction is avoided, both intramedullary and extramedullary implants will maintain the fracture reduction and resist failure. This will allow early weight bearing of patients, whether they are operated upon by intramedullary or extramedullary implant. The cost of cephalomedullary devices is generally more than sliding hip screw fixation in most institutions. Cephalomedullary nail fixation reduces the length of hospital stay and fewer complications (Xu 2018), which can decrease the overall costs with cephalomedullary devices.
Cephalomedullary device – unstable intertrochanteric fractures
Recommendation:
In patients with unstable intertrochanteric fractures, the use of cephalomedullary device is recommended. (Strong recommendation, High quality evidence)
Remarks
Unstable trochanteric fractures are fractures with comminution, posteromedial fragment, deficient lateral wall, reversed oblique, and subtrochanteric extension. This fracture pattern is considered unstable as it will drift into varus and/or medialization with exposure to compressive loads.
Summary of evidence
In a systematic review and meta-analysis conducted by Zeelenberg ML et al. (2024)83, current literature shows that several functional outcomes, complications, and surgical outcomes were statistically in favor of intramedullary fixation when compared with extramedullary fixation of AO/OTA 31-A2 fractures. However, as several of the differences found appear not to be clinically relevant and for many outcomes data remains sparse or heterogeneous, complete superiority of IM fixation for AO type 31-A2 fractures remains to be confirmed.
Kassem et al. (2022)84, in another systematic review and meta-analysis to compare DHS with trochanter stabilizing plate (TSP) and short proximal femoral nails (PFNs) in unstable trochanteric fractures in terms of the functional and radiological outcomes. They concluded that the use of PFN in unstable trochanteric fractures was associated with a shorter time until union and a faster return to the pre-fracture level of activity than the DHS+TSP. However, postoperative hip function, walking independence, as well as complication and one-year mortality rates were comparable. Based on these findings, they suggested that PFN is the first-choice implant for the unstable (AO/OTA 31-A2) intertrochanteric fractures.
Lewis et al. (2022), in a systematic review, included older adults with both stable and unstable extracapsular fractures. Their findings indicate that there may be no difference between cephalomedullary nails versus dynamic fixed-angle plates
Proximal femoral locking compression plate versus intramedullary nailing for unstable intertrochanteric fracture
Zhong B et al. (2014)82 concluded that in unstable intertrochanteric fractures, the value of PFLCP fixation needs to be confirmed by further clinical studies. Fixation with an intramedullary nail is still the best option for patients with unstable intertrochanteric fractures; however, controlled studies are needed.
Zhang S et al. (2025)85 conducted a systematic review and meta-analysis of randomized controlled trials with the aim of summarizing the latest evidence for the effectiveness and safety of a variety of implants for fixation of intertrochanteric fractures. They concluded that InterTAN nail (ITN) clearly reduces the incidence of non-mechanical major post-surgery complications and non-specific mechanical complications; however, it is associated with an increased risk of intraoperative complications. No differences were observed between SHS and other implants regarding Harris hip score, reoperation rate, and overall mechanical complications. Most comparisons evaluating the efficacy of these implants are supported by moderate confidence of evidence. Further large-scale, longitudinal, randomized controlled trials are necessary to provide more robust and consistent evidence.
Rationale for the recommendation
Unstable intertrochanteric fractures are fractures that may have comminution, posteromedial fragment, deficient lateral wall, reversed oblique, or subtrochanteric extension. This fracture pattern is considered unstable as it will drift into varus and/or medialization with exposure to compressive loads. Fixation with an intramedullary nail is still the best option for patients with unstable intertrochanteric fractures, as it is biomechanically superior to an extramedullary implant.
Cephalomedullary device – subtrochanteric/reverse obliquity fractures
Recommendation:
In patients with subtrochanteric or reverse obliquity fractures a cephalomedullary device is recommended. (Strong recommendation, High quality evidence)
Remarks
Reverse obliquity fractures are a subset of intertrochanteric/peritrochanteric fractures that are an unstable pattern. Though subtrochanteric fractures are more of a proximal femur fracture, they can be a component of an intertrochanteric fracture as well.
Summary of evidence
Xie et al. (2019) 86 in a meta-analysis suggested that intramedullary fixation for subtrochanteric fracture might be superior to extramedullary fixation in terms of shorter operation time, less intraoperative blood loss, shorter length of incision, length of stay, and better functional outcomes. Meanwhile, intramedullary fixation had a lower rate of fixation failure and reoperation. Therefore, intramedullary fixation is recommended as the treatment of subtrochanteric fractures. Larger multi-centre and high-quality RCTs are required for further research.
The results of a meta-analysis conducted by Wang J et al. (2020)87 revealed that intramedullary fixation can confer shorter union time, lower non-union, and reoperation rates compared with extramedullary fixation. They considered intramedullary nailing as the first selection for the treatment of patients with subtrochanteric fractures.
Plating may be considered in select cases, such as periprosthetic fractures, proximal deformities, or salvage situations.88
Rationale for the recommendation
Intramedullary nailing is the implant of choice in subtrochanteric fractures and reverse obliquity fractures. It is biomechanically superior to a surface implant.
Blood transfusion
Recommendation
A blood transfusion threshold of no higher than 8g/dl is suggested in asymptomatic postoperative hip fracture patients. (Conditional recommendation, Moderate quality evidence)
Remarks
Moderate-strength evidence suggests that restrictive transfusion practices reduce utilization of transfusions and may decrease infections without increasing adverse outcomes in major orthopaedic surgery. 89-93
Initial Assessment
1. Hemodynamic status (stable/unstable)
2. Haemoglobin (Hb) level
3. Symptoms of anaemia (tachycardia, hypotension, dyspnoea, chest pain, dizziness)
4. Cardiovascular comorbidities
Decision Nodes
· Hb < 8 g/dL → transfuse
· Hb 8–10 g/dL → transfuse if symptomatic or high cardiac risk
· Hb >10 g/dL → no transfusion, monitor
Transfusion Strategy
· Restrictive strategy preferred
· Number of units per transfusion (usually 1 unit at a time, reassess Hb)
· Monitor for transfusion reactions
Reassessment
· Post-transfusion Hb
· Re-evaluate symptoms
· Repeat transfusion only if Hb < 8 g/dL or persistent symptoms
Pre-op Optimization
· Ensure hemodynamic stability
· Correct coagulopathy if present
· Proceed to surgery once stable
Optional Branches
· Non-operative/palliative care for patients with limited life expectancy or refusal of transfusion
· Consider erythropoietin or iron supplementation if appropriate
Refusal of blood transfusion
When an elderly hip-fracture patient needs transfusion but refuses 93-96
1. Confirm capacity & informed refusal
· Assess and document decision-making capacity.
· Clearly explain:
· Why blood may be needed
· Risks of refusing transfusion (anaemia, cardiac events, death)
· Available alternatives
· Obtain written informed refusal (ideally with a witness).
· If the patient lacks capacity → follow advance directives or legally authorized surrogate.
If the patient has capacity, their refusal must be respected, even if life-threatening.
2. Clarify what is acceptable
Many patients who refuse “blood” may accept:
· Cell salvage (closed circuit)
· Acute normovolaemic haemodilution
· Albumin
· Coagulation factors (e.g., fibrinogen, PCC)
· Erythropoietin
· Iron therapy
Do not assume refusal of all blood products — ask and document precisely.
3. Optimize pre-operative haemoglobin
If surgery can be delayed safely (24–48 h max in hip fractures):
· IV iron (e.g., ferric carboxymaltose)
· Erythropoietin (EPO)
· Folic acid + vitamin B12
· Minimize blood sampling
4. Choose the least blood-loss strategy
Surgical
· Prefer hemiarthroplasty over THA when appropriate
· Cemented stems (shorter operative time)
· Meticulous haemostasis
· Minimize operative time
Anaesthetic
· Regional anaesthesia (spinal) if feasible
· Controlled hypotension (careful in elderly)
· Tranexamic acid (TXA) — IV ± topical
5. Intra- and post-operative blood conservation
· TXA significantly reduces blood loss in hip fracture surgery
· Cell salvage if acceptable
· Maintain normothermia
· Restrictive transfusion thresholds (already transfusion-free)
6. Post-operative management
· Tolerate lower Hb if patient is asymptomatic
· Oxygen therapy
· Treat anaemia aggressively with iron/EPO
· Early mobilization to reduce complications
7. Ethical & legal principles
· Autonomy overrides beneficence in a competent adult
· Forced transfusion = assault
· Thorough documentation protects both patient and physician
· Involve:
· Ethics committee (if available)
· Hospital legal team (high-risk cases)
Summary of evidence
A restrictive red blood cell transfusion strategy is supported by high-quality evidence in elderly patients with hip fractures. Randomized controlled trials, including the FOCUS trial92, demonstrated that transfusing asymptomatic patients only when hemoglobin falls below 8g/dL does not increase mortality, cardiovascular complications, functional recovery impairment, length of hospital stay, or loss of independent ambulation compared with a liberal transfusion strategy.
International guidelines, including those from the AABB93, NICE91, and AAOS2, therefore recommend a restrictive transfusion threshold for most elderly hip fracture patients, while emphasizing that symptomatic anemia, ongoing bleeding, hemodynamic instability, or evidence of tissue hypoxia may justify transfusion at higher hemoglobin levels.
For patients who decline blood transfusion, patient blood management measures such as intravenous iron, erythropoietin, tranexamic acid, meticulous surgical hemostasis, minimization of phlebotomy, optimization of oxygen delivery, and early mobilization are recommended to reduce transfusion requirements.
The evidence supporting a restrictive transfusion threshold in elderly hip fracture patients2,7,91-93,97,98 is considered high quality, with strong consistency across randomized trials and major international guidelines.
Rationale for the recommendation
A restrictive transfusion strategy is recommended for most elderly patients with hip fractures. Current high-quality evidence demonstrates that using a haemoglobin threshold of 8 g/dL (unless the patient is symptomatic or has ongoing bleeding) is safe and effective. Compared with a liberal transfusion strategy, it does not increase:
· 30- or 60-day mortality
· Cardiovascular complications
· Functional recovery
· Independent walking ability
· Length of hospital stay
· Discharge destination
Restrictive transfusion also reduces unnecessary exposure to blood products and transfusion-related complications while conserving healthcare resources (Annex 7: Blood transfusion in elderly hip fracture patients (flowchart)).
Tranexamic acid
Recommendation
Tranexamic acid should be administered to reduce blood loss and blood transfusion in patients with hip fractures. (Strong recommendation, High quality evidence)
Remarks
Tranexamic acid was not associated with higher incidence of mortality or symptomatic thromboembolic events.
1. Assess Patient Eligibility
· Confirm hip fracture requiring surgery (intracapsular or extracapsular)
· Age > 65 years
· Check for contraindications:
o Active thromboembolic disease (DVT, PE)
o History of stroke or myocardial infarction within 6 months
o Active intravascular clotting disorder
o Known hypersensitivity to TXA
o Severe renal impairment
2. Decide on Route and Dose
· IV TXA is preferred
· Typical regimen:
o Bolus: 1 g IV preoperatively (within 30 min before incision)
o Optional second dose: 1 g IV postoperatively or infusion over 8 hours in high-risk bleeding patients
· Adjust dose for renal impairment
3. Timing of Administration
· Preoperative: ideally at induction of anaesthesia
· Some protocols allow additional intraoperative/topical dose if significant bleeding risk
4. Monitor Patient
· Watch for thromboembolic complications
· Monitor haemoglobin postoperatively
· Assess need for transfusion
5. Postoperative Considerations
· Early mobilization
· Thromboprophylaxis as per institutional protocol (e.g., LMWH or DOAC)
· Reassess bleeding risk and renal function
6. Contraindicated Patients
· Avoid TXA if active clotting risk or severe renal impairment
· Consider alternative blood conservation strategies
Summary of evidence
High-quality evidence demonstrates that tranexamic acid (TXA) significantly reduces perioperative blood loss and the need for allogeneic blood transfusion in elderly patients undergoing hip fracture surgery without increasing the risk of venous thromboembolism (VTE), myocardial infarction, stroke, or all-cause mortality99-101.
Multiple randomized controlled trials102 and meta-analyses99-101 have consistently shown reductions in total blood loss (approximately 200–400 mL) and transfusion rates (relative reduction of approximately 30–50%) compared with placebo or standard care. These benefits are observed across different surgical procedures, including hemiarthroplasty, total hip arthroplasty for fracture, and internal fixation.
Current evidence indicates that both intravenous and topical TXA are effective. Intravenous administration is supported by the largest body of evidence, while topical TXA provides a reasonable alternative when systemic administration is contraindicated. No clear superiority of one route over the other has been demonstrated.
Large observational studies and systematic reviews have found no significant increase in symptomatic deep vein thrombosis, pulmonary embolism, myocardial infarction, stroke, or mortality when TXA is used in appropriately selected patients receiving standard thromboprophylaxis.
Based on the consistency of evidence, major international organizations, including the American Academy of Orthopedic Surgeons (AAOS)2 and the National Institute for Health and Care Excellence (NICE)7, recommend considering routine TXA administration in hip fracture surgery unless contraindications exist.
Strength of Evidence
|
Outcome |
Quality of Evidence |
Overall Conclusion |
|
Reduction in perioperative blood loss |
High |
Significant reduction |
|
Reduction in blood transfusion |
High |
Significant reduction |
|
Reduction in postoperative hemoglobin drop |
High |
Significant benefit |
|
Risk of DVT/PE |
High |
No significant increase |
|
Risk of myocardial infarction or stroke |
Moderate–High |
No significant increase |
|
Mortality |
Moderate |
No increase in mortality |
|
Length of hospital stay |
Moderate |
Little or no consistent benefit |
Guideline Statement
High-certainty evidence supports the use of tranexamic acid in elderly patients undergoing hip fracture surgery. TXA consistently reduces perioperative blood loss and transfusion requirements without increasing thromboembolic or cardiovascular complications when used with standard venous thromboembolism prophylaxis. Therefore, routine perioperative administration of TXA should be considered in the absence of contraindications (Annex 8: Tranexamic acid (TXA) in elderly hip fracture patients).
Rationale for the recommendation
Patients with hip fractures may benefit from TXA to reduce blood loss and subsequent transfusion. Use of tranexamic acid in hip fracture patients may result in lower blood loss and transfusion rates compared to placebo in several high-quality studies. Studies were unable to detect any difference in adverse events with use of tranexamic acid such as infection, wound complication, DVT, CVA, PE or MI7,37,102-107
Interdisciplinary care programs
Recommendation
On admission, offer patients a formal, acute orthogeriatric or orthopaedic ward-based fracture program that includes the following steps:
· Comprehensive orthogeriatric assessment to evaluate both current and baseline level of functioning
· Rapid optimization to make patient fit for surgery
· Identify individual goals for multidisciplinary rehabilitation to recover mobility and independence, and to achieve return to pre-fracture residence when possible
· Offer longitudinal, coordinated, orthogeriatric and multidisciplinary review
· Provide liaison or integration with related services, particularly mental health (delirium prevention), falls prevention, bone health, primary care and social services
· Clinical and service governance responsibility for all stages of the pathway of care and rehabilitation, including those provided in the community.
(Conditional recommendation, High quality evidence)
Remarks
Hip Fracture Program (HFP):
It is a comprehensive interdisciplinary evidence-based model of immediate and longitudinal interdisciplinary assessment, management and discharge planning7. Instead of the traditional model of orthopaedic care followed by routine transfer for rehabilitation elsewhere (e.g. orthopaedic or general rehabilitation units), interdisciplinary model provides many benefits including expediting and organizing both assessment and care in the acute hospital, promoting prompt discharge (wherever possible) to the patient’s normal home setting. It is more cost-effective compared to traditional model as established following the latest NICE CG124 (Clinical Guideline 124) evidence review7,108.
Prompt, effective analgesia, anaesthesia and surgery, coordinated with structured, medical and multidisciplinary management from presentation to hospital discharge, are therefore needed and have been shown to deliver improved outcomes cost-effectively7.
The medical and multidisciplinary ‘ortho-geriatrician’ role was developed by physicians in clinical gerontology but is applicable to the care of hip fractures in adults of all ages109.
Summary of evidence
A RCT (Randomized Clinical Trial)110 of 199 patients analysed admittance to a geriatric rehabilitation ward (comprising a geriatric team applying comprehensive geriatric assessment) versus regular orthopaedic care immediately postoperative to hip fracture surgery. Patients randomized to geriatric ward had less postoperative delirium (being shorter in those who developed it), fewer pressure ulcers, less malnutrition, fewer urinary tract infections, fewer falls, fewer new fractures during hospitalization, shorter hospital length of stay, and a 3-fold odds ratio of walking independently 1 year after. They also found that the best effect was seen in patients with dementia.
Another RCT111 of 459 patients with hip fracture compared orthogeriatric co-management versus care by a geriatric consultant team versus standard orthopaedic care. Compared with standard care and geriatric consultant team care, orthogeriatric care showed significantly better outcomes in terms of time-to-surgery and in-hospital medical complications. Versus standard care, orthogeriatric care was also associated with significant reductions in hospital length of stay and in-hospital mortality.
Rationale for the recommendation
Ortho-geriatric team involvement in care provision for hip fracture patients from admission to discharge reduces complications, improves both in-hospital and long-term outcomes and reduces cost of care.
Postoperative Rehabilitation
1. Timing of
Mobilization
Recommendation
In patients undergoing surgical stabilization of hip fractures, early mobilization, including functional movement within 24–48 hours postoperatively is recommended, provided the patient is medically and mobilization is consistent with the surgeon’s postoperative instructions (Strong recommendation, High quality evidence)
Remarks
Mobilization should begin with bed mobility and progress to sitting, standing, and assisted ambulation as tolerated. Progression should be individualized according to pain levels, hemodynamic stability, cardiopulmonary status, and overall medical condition. Delays in mobilization may be necessary in cases of medical instability but should be minimized whenever possible.
Summary of evidence
Multiple randomized controlled trials112 and systematic reviews113,114 have consistently demonstrated that early mobilization following hip fracture surgery is associated with reduced postoperative complications, including pneumonia, thromboembolic events, delirium, and pressure injuries. Early mobilization has also been shown to improve functional recovery, reduce length of hospital stay, and enhance the likelihood of returning to pre-fracture mobility levels. Across studies, mobilization initiated within the first 24–48 hours is superior to delayed mobilization strategies.
Rationale for the recommendation
Early mobilization mitigates the adverse physiological effects of prolonged bed rest, supports cardiovascular and pulmonary function, and promotes neuromuscular activation necessary for recovery of mobility, independence, and overall functional outcomes.
2. Weight-Bearing
Recommendation
Following hip fracture surgery, weight-bearing should be initiated as early as clinically feasible, with full weight-bearing as tolerated recommended after stable fixation, unless contraindicated by surgical or patient-specific factors (Conditional recommendation, Low quality evidence)
Remarks
In cases of uncertain fixation stability, complex fracture patterns, or compromised bone quality, temporary partial or restricted weight-bearing may be considered. Decisions should be guided by operative findings, implant stability, surgeon recommendations, patient cognitive status, and safety within the rehabilitation environment.
Summary of evidence
Available evidence, primarily from observational studies115 and cohort analyses2,116-118, suggests that early weight-bearing after stable fixation does not increase the risk of implant failure, non-union, or reoperation. Several studies report improved functional outcomes and earlier return to ambulation with early weight-bearing strategies119. However, high-quality randomized controlled trials specifically comparing weight-bearing protocols after hip fracture surgery remain limited.
Rationale for the recommendation
Early weight-bearing facilitates functional recovery, improves patient confidence during ambulation, and reduces complications related to immobility, while allowing clinicians to individualize care based on surgical stability and patient safety considerations.
3. Rehabilitation Pathway
Recommendation
Rehabilitation after hip fracture surgery should follow a structured, phased pathway, spanning the acute inpatient phase, home or inpatient rehabilitation services, and outpatient rehabilitation, aligned with the patient’s recovery stage and care setting (Conditional recommendation, Low Quality evidence)
Remarks
The rehabilitation pathway should prioritize early mobility and functional independence during hospitalization, followed by progressive strengthening, balance training, and gait restoration after discharge. Coordination among healthcare providers across settings is essential to ensure continuity of care.
Summary of evidence
Studies evaluating multidisciplinary and continuity-based rehabilitation models120,121 demonstrate improvements in mobility, functional outcomes, and discharge disposition. However, variability in rehabilitation protocols, intensity, and care settings limits the ability to identify a single optimal pathway. Evidence supports the concept of structured progression rather than any specific standardized protocol.
Rationale for the recommendation
A structured rehabilitation pathway ensures continuity of care, promotes timely progression of functional goals, optimizes resource utilization, and addresses the evolving physical and functional needs of patients recovering from hip fractures.
4. Fall Prevention
Recommendation
Fall prevention strategies should begin with identification and management of underlying fall risk factors, including muscle weakness, balance deficits, cognitive impairment, medication-related side effects, orthostatic hypotension, visual impairment, and environmental hazards. These strategies should be systematically integrated into all phases of postoperative rehabilitation following hip fracture surgery (Conditional recommendation, High quality evidence)
Remarks
Fall prevention interventions should include fall risk assessment, balance and strength training, home based exercise program, medication review, environmental hazard modification, vision assessment, and appropriate prescription and training in assistive device use.
Summary of evidence
Strong evidence from randomized controlled trials and meta-analyses122-124 demonstrates that multifactorial fall prevention programs significantly reduce fall risk in older adults. Although many studies include broader geriatric populations, evidence supports similar benefits in individuals recovering from hip fracture, who are at particularly high risk for recurrent falls and secondary fractures.
Rationale for the recommendation
Patients recovering from hip fractures are vulnerable to recurrent falls due to residual weakness, balance impairment, and fear of falling. Addressing modifiable risk factors is essential to ensure long-term safety, preserve functional gains, and prevent secondary injuries.
5. Outcome Assessment
Recommendation
Standardized functional and mobility outcome measures, such as the Timed Up and Go Test (TUG test), should be used regularly to guide rehabilitation progression and monitor recovery after hip fracture surgery. (Conditional recommendation, Low quality evidence)
Remarks
Outcome measures should be feasible, clinically meaningful, and sensitive to change in older adults. Assessments may include measures of mobility, balance, gait performance, activities of daily living, and pain.
Summary of evidence
Although outcome measures such as gait speed, Timed Up and Go, and functional mobility scales are widely used in clinical practice and research, evidence supporting the superiority of any single tool in guiding rehabilitation outcomes remains limited. Current evidence125,126 supports consistent and repeated use of standardized measures rather than reliance on subjective assessment alone.
Rationale for the recommendation
Regular outcome assessment facilitates individualized goal setting, enhances communication among care providers, and allows early identification of delayed recovery, complications, or need for modification of the rehabilitation plan.
6. Discharge Planning After Hip Fracture Surgery
Recommendation
Discharge planning should begin early during hospitalization and be individualized based on medical stability, functional recovery, cognitive status, family support, and access to rehabilitation services. In the Egyptian healthcare setting, most patients require a short inpatient stay followed by home-based or facility-based rehabilitation. Early discharge within 24–48 hours may be considered for selected, medically stable patients with adequate family support and rehabilitation access. Same-day or next-day discharge should be limited to exceptional cases. (Conditional recommendation, Low quality evidence)
Remarks
Discharge planning should address discharge destination, functional readiness (safe transfers and assisted ambulation), caregiver education, provision of walking aids, and coordination of outpatient or home-based rehabilitation. Family caregivers play a central role in post-discharge care in Egypt and should be included early in planning and education.
Summary of evidence
Hip fracture specific randomized evidence for same-day discharge is limited. Observational studies indicate that structured, early discharge planning improves care transitions and functional outcomes without increasing readmissions when rehabilitation continuity is ensured. Evidence from elective arthroplasty populations shows that same-day or 1-day discharge can be safe in selected patients, supporting a readiness-based rather than time-based discharge approach, though direct extrapolation to hip fracture patients should be cautious127,128.
Rationale for the recommendation
Early and coordinated discharge planning reduces risks associated with prolonged hospitalization, including delirium and deconditioning, and supports safe transition to rehabilitation. Discharge timing should prioritize patient safety, caregiver preparedness, and continuity of rehabilitation rather than length of stay alone.
7. Assistive Devices (Walker and Cane)
Recommendation
Following hip fracture surgery, appropriate assistive devices should be prescribed and regularly reassessed to support safe ambulation. A walker is recommended in the early postoperative phase, with progression to a cane held in the contralateral hand to the operated limb as balance, strength, and weight-bearing tolerance improve. (Good practice statement, Low quality evidence)
Remarks
Assistive device selection should be individualized based on balance capacity, lower-limb strength, pain, cognitive status, and environmental demands. Proper fitting, patient education, and supervised training are essential. Transition from a walker to a cane should be guided by functional performance rather than time since surgery alone.
Summary of evidence
Systematic reviews and biomechanical studies demonstrate that walkers provide greater stability during early postoperative ambulation, while cane use improves gait efficiency during later recovery. Biomechanical evidence consistently shows that using a cane in the contralateral hand reduces hip joint reaction forces and hip abductor demand on the operated side. Clinical practice guidelines support this progression strategy, although randomized controlled trials specific to hip fracture populations remain limited126,129.
Rationale for the recommendation
Assistive devices enhance safety and confidence during ambulation after hip fracture surgery. Using a cane in the contralateral hand optimizes biomechanical unloading of the operated hip, improves gait symmetry, and reduces fall risk while promoting progressive independenc
Patient and carer information
Recommendation
It is crucial to offer the patients (or when appropriate, their carers) information about their medical diagnosis and its implications and treatment options and management plan either verbally or in printed form (Good practice statement).
Remarks
Family, friends and carers can provide support to patients to prepare for the first few weeks after discharge. From simple tasks like measuring the heights of patient’s bed, toilet and chair to providing physical and emotional support, the role of carers is important for the patients.
Decision making process must be based on information, involving family and carers can be crucial in cases where the patient is incapacitated due to delirium and can help as proxy in making informed medical decisions.
Summary of evidence
The care burden following hip fracture may decrease over time; however, it often lasts for over 12 months. Caregivers tend to experience the greatest stress for the first 2 months post-fracture, with the stress being associated with increased care demands and care cost130-133. Educating them beforehand sets realistic expectation to carers.
Rationale for the recommendation
Providing clear information to patients and carers supports shared decision-making, treatment adherence, realistic expectations, and active participation in rehabilitation, ultimately contributing to safer and more patient-centred care. Details should include their exact diagnosis, choices available for analgesia and other medications, surgical procedures, choices of anaesthesia, possible complications, postoperative care and rehabilitation plans, short and long term expected outcomes and which healthcare professionals are involved7.
- Acknowledgement
We would like to acknowledge the “Hip Fractures in the Elderly” Sub-Group of the Egyptian Orthopaedic Guidelines (EOG) Scientific Committee for developing these guidelines.
Chair of the EOG Scientific
Committee:
Adel Adawy, Professor of
Orthopaedic Surgery, Benha University – Former Health Minister
Members of the “Hip Fractures in the Elderly” Guideline Development Group (arranged alphabetically):
|
Amany Ezzat Ayad |
Professor of Anaesthesia, ICU and Pain, Cairo University |
|
Elsayed Morsi Zaki Mohamed |
Professor of Orthopaedic surgery, Menoufia University |
|
Emad Samuel Boles Saweeres |
Professor and Chairman of Orthopaedic Advisory Committee, The General Organisation for Teaching Hospitals and Institutes |
|
Mariam Abdel Azim Ibrahim |
Orthopaedic Physical Therapist, Assiut University |
|
Mohamed Saleh Moustafa Hassan |
Professor of Orthopaedic Surgery, Suez Canal University, Ismailia |
|
Osama Ahmed Farouk |
Professor of Orthopaedic Surgery, Assiut University Trauma Hospital, Faculty of Medicine, Assiut University |
|
Samia Ahmed Abdul-Rahman |
Professor of Geriatrics and Gerontology, Ain Shams University |
|
Sherif Ishak Azmy Kheir |
Professor of Orthopaedic Surgery, Ain Shams University |
- Abbreviations
AP = Antero-posterior
ASRA = American Society of Regional Anaesthesia and Pain Medicine
BCIS = Bone Cement Implantation Syndrome
CK = Creatine kinase
CVA =Cerebrovascular Accident
DA = Direct anterior approach
DVT = Deep Vein Thrombosis
ESAIC = European Society of Anaesthesiology and Intensive Care
ESRA = European Society of Regional Anaesthesia
FICB = Fascia iliaca block
FLACC scale = Face, Legs, Activity, Cry, Consolability scale
FNB = Femoral nerve block
HA = Hemiarthroplasty
HFP= Hip Fracture Program
LR = Likelihood Ratio
MI = Myocardial Infarction
MIS = Minimally invasive surgery
PE = Pulmonary Embolism
PENG = Pericapsular Nerve Group
QUADAS-2 = Quality Assessment of Diagnostic Accuracy Studies tool
RCT = Randomized Controlled Trial
THA = Total Hip Arthroplasty
VTE = Venous Thromboembolism
- Glossary
· Ambulatory: Able to walk 10 meters or more indoor with or without assistive device prior fracture and able to walk independently out of doors with no more than the use of a stick and do not have a condition or comorbidity that makes the procedure unsuitable for them.
· Early mobilization: The initiation of functional movement and physical activity as soon as medically and surgically appropriate following injury, illness, or surgery, often within the first 24–48 hours. It may include sitting, standing, transfers, and assisted ambulation depending on the patient’s condition and clinical recommendations.
· Fragility fracture: These are fractures which result from low-energy trauma (a mechanical force that would not ordinarily cause a fracture), such as a fall from standing height or less. These fractures are the main clinical consequence of osteoporosis, although they may occur in postmenopausal women even in the absence of osteoporosis.
· Interdisciplinary care: It is a team which consist of health care professionals from different disciplines who provide coordinated, integrated care with collectively set goals and shared resources and responsibilities.
· Medically optimized: Cleared by anaesthesia
· Neuraxial / deep, non-compressible procedures: spinal/epidural and deep plexus or deep peripheral blocks at non-compressible sites (treated like neuraxial for timing decisions).
· Older patient/adult typically age 60+; however, frailty and comorbidity burden are more important than chronological age.
· Stable femoral neck fracture: In patients with stable (impacted/non-displaced Garden’s I and II) femoral neck fractures
· Stable trochanteric fracture: Stable trochanteric fractures are simple two-part intertrochanteric fractures with posteromedial cortical continuity and lateral wall integrity. This fracture pattern is considered stable as it will resist medial compressive loads once reduced.
· Superficial / compressible single-shot blocks: peripheral blocks at compressible sites (e.g., fascia iliaca plane, femoral, adductor canal). Decisions should be based on site-specific bleeding risk assessment.
· Unstable femoral neck fracture: displaced intracapsular fractures in which the proximal fragment contains the femoral head with or without a portion of the femoral neck and contained within the capsule and radiologically confirmed Garden type III or IV.
· Unstable trochanteric fracture: Unstable trochanteric fractures are fractures with comminution, posteromedial fragment, deficient lateral wall, reversed oblique, and subtrochanteric extension. This fracture pattern is considered unstable as it will drift into varus and/or medialization with exposure to compressive loads.
- Introduction
Hip fractures represent a major public health challenge and are among the most serious consequences of osteoporosis and falls in older adults. They are associated with substantial morbidity, mortality, loss of independence, reduced quality of life, and increased healthcare utilization. With an aging population, the incidence of hip fractures is expected to continue rising, placing an increasing burden on healthcare systems and society1,2.
Optimal outcomes following hip fracture depend on timely diagnosis, appropriate surgical management, comprehensive perioperative care, early mobilization, multidisciplinary rehabilitation, and secondary fracture prevention. However, variations in clinical practice and institutional protocols may lead to inconsistencies in patient assessment, treatment selection, perioperative management, and rehabilitation, ultimately affecting patient outcomes3,4.
Management of displaced intracapsular hip fractures, particularly completely displaced femoral neck fractures, remains an important area where treatment strategies may differ between institutions. Standardized, evidence-based recommendations are therefore essential to ensure that patients receive the most appropriate intervention based on current evidence, patient characteristics, functional status, and surgical expertise5,6.
These Egyptian
Guidelines for the Management of Hip Fractures have been developed to provide
evidence-based, multidisciplinary recommendations for the assessment and
management of adults with hip fractures. The guidelines aim to standardize care
across healthcare settings in Egypt, improve patient outcomes, reduce
complications, optimize resource utilization, and promote functional recovery
and secondary fracture prevention.
- Scope and purpose
These Egyptian Guidelines provide evidence-based recommendations for the multidisciplinary management of adults with hip fractures, from initial presentation through definitive treatment, rehabilitation, and secondary fracture prevention. The guideline covers the assessment and management of intracapsular and extracapsular hip fractures, including recommendations for surgical decision-making, perioperative optimization, anaesthesia, pain management, blood transfusion, thromboprophylaxis, postoperative rehabilitation, orthogeriatric care, osteoporosis management, and discharge planning.
The primary objectives of these guidelines are to:
· Standardize evidence-based hip fracture care across healthcare institutions in Egypt.
· Support appropriate surgical decision-making, including indications for internal fixation and arthroplasty in patients with femoral neck fractures.
· Promote timely surgery and optimization of physiological status before surgery.
· Provide recommendations for perioperative management, including pain control, regional anaesthesia, blood management, and thromboprophylaxis.
· Facilitate early mobilization, multidisciplinary rehabilitation, and restoration of functional independence.
· Reduce complications, mortality, hospital length of stay, and unnecessary healthcare costs.
These guidelines are designed to provide practical, evidence-informed recommendations that can be implemented across a wide range of healthcare settings while allowing clinicians to individualize management according to patient characteristics, comorbidities, available resources, and clinical judgment.
- Target audience
These guidelines are intended for healthcare professionals involved in the care of patients with hip fractures, including:
· Orthopaedic surgeons
· Geriatricians
· Anaesthesiologists
· Emergency medicine physicians
· Physiotherapists
· physiatrist
· Nursing staff
· Clinical pharmacists
· Radiologists
- Methods
A comprehensive search for guidelines was undertaken to identify the most relevant guidelines to consider for adaptation.
Inclusion/ exclusion criteria followed in the search and retrieval of guidelines to be adapted:
• Selecting only evidence-based guidelines (guideline must include a report on systematic literature searches and explicit links between individual recommendations and their supporting evidence)
• Selecting only national and/or international guidelines
• Specific range of dates for publication (using Guidelines published or updated in the last 3 years)
• Selecting peer reviewed publications only
• Selecting guidelines written in English language
• Excluding guidelines written by a single author, not on behalf of an organization to be valid and comprehensive, a guideline ideally requires multidisciplinary input
• Excluding guidelines published without references as the panel needs to know whether a thorough literature review was conducted and whether current evidence was used in the preparation of the recommendations
The following characteristics of the retrieved guidelines were summarized in:
• Developing organization/authors
• Date of publication, posting, and release
• Country/language of publication
• Date of posting and/or release
• Dates of the search used by the source guideline developers
All retrieved Guidelines were screened and appraised using AGREE II instrument (www.agreetrust.org) by at least three members. The panel decided on a cut-off point or ranked the guidelines (any guideline scoring above 50% on the rigor dimension was retained). The GDG decided to adapt the NICE CG124 (2025 update)7 hip fracture management guideline and the AAOS Clinical Practice Guideline Summary2: Management of Hip Fractures in Older Adults.
- Evidence assessment
According to WHO Handbook for Guidelines, we used the GRADE (Grading of Recommendations, Assessment, Development and Evaluation) approach to assess the quality of a body of evidence, develop and report recommendations. GRADE methods are used by WHO because these represent internationally agreed standards for making transparent recommendations. Detailed GRADE information is available on the following sites:
• GRADE working group: https://www.gradeworkinggroup.org
• GRADE online training modules: https://macgrade.mcmaster.ca/grade-learning-hub/grade-for-guideline-development/
• GRADE profile software: https://www.gradepro.org
Quality of evidence was rated according to criteria in Table 1. Significance of the four levels of evidence and factors that determine how to upgrade or downgrade the quality of evidence are illustrated in Annex 1: GRADE’s approach to rating quality of evidence 8
Table 1: Quality of evidence in GRADE
Quality level | Definition |
High | We are very confident that the true effect lies close to that of the estimate of the effect. |
Moderate | We are moderately confident in the effect estimate: the true effect is likely to be close to the estimate of the effect, but there is a possibility that it is substantially different. |
Low | Our confidence in the effect estimate is limited: the true effect may be substantially different from the estimate of the effect. |
Very low | We have very little confidence in the effect estimate: the true effect is likely to be substantially different from the estimate of effect. |
The strength of the recommendation
The strength of a recommendation communicates the importance of adherence to the recommendation.
Strong recommendations
With strong recommendations, the guideline communicates the message that the desirable effects of adherence to the recommendation outweigh the undesirable effects. This means that in most situations the recommendation can be adopted as policy.
Conditional recommendations
These are made when there is greater uncertainty about the four factors above or if local adaptation has to account for a greater variety in values and preferences, or when resource use makes the intervention suitable for some, but not for other locations. This means that there is a need for substantial debate and involvement of stakeholders before this recommendation can be adopted as policy.
When not to make recommendations
When there is lack of evidence on the effectiveness of an intervention, it may be appropriate not to make a recommendation.
- Clinical indicators for monitoring
Different healthcare systems around the world monitor implementation of their hip fracture management guideline recommendations in elderly through various Key Performance Indicators (KPIs). This section contains suggested KPIs for Egyptian hip-fracture care based on the above guidelines. It is the belief of the Guideline Development Group (GDG) that inclusion of as many of the suggested KPIs as one of the Presidential Healthcare Initiatives is the best way to monitor performance of different hospitals/healthcare regions or organization and insure implementation of best practice across the country. The GDG members are ready to contribute to such initiatives upon request.
A. Registry and case capture KPIs:
Without complete case capture, outcome comparisons are unreliable. The Fragility Fracture Network (FFN) recommends an audit dataset for countries starting hip-fracture registries (https://fragilityfracturenetwork.org)
· Case capture rate: The percentage of all patients aged 60 or older with a low-energy hip fracture who are entered into a local or national registry.
· Minimum dataset completeness: The percentage of records that include complete information about age, sex, residence, mobility, cognitive status, ASA, fracture type, operation, surgery time, and discharge status.
· Pre-fracture function documented: The percentage of patients with documented pre-fracture mobility/ADL and cognitive function.
B. Emergency department and preoperative KPIs:
· Time from hospital arrival to X-ray/diagnosis: The median time from the emergency department (ED) arrival to the confirmed diagnosis.
· Pain assessment: The percentage of patients with documented pain scores at presentation and repeatedly after administration of analgesia.
· Analgesia within 30 minutes: The percentage of patients who receive appropriate analgesia within 30 minutes of arrival or diagnosis.
· Preoperative medical optimization: The percentage of patients with anaemia, anticoagulation, dehydration, electrolytes, diabetes, heart failure, arrhythmia/ischemia, or chest infection assessed and addressed promptly.
C. Surgical-timing KPIs:
· Surgery within 48 hours of presentation: The percentage of patients who are operated on within 48 hours of arrival at the operating hospital.
· Reason for surgical delay documented: The percentage of delayed cases with documented medical or systemic reasons for the delay.
· Planned trauma list access: The percentage of cases that are done on the planned trauma/urgent orthopaedic list, not repeatedly postponed by elective work.
· Senior surgeon/anaesthetist involvement: The percentage of cases that are supervised or performed by a consultant or senior-trained surgeon and anaesthetist.
D. Orthogeriatric/medical co-management KPIs:
· Orthogeriatric/physician review: Geriatrician, internist, or trained perioperative physician review within 24 hours.
· Cognitive impairment/delirium risk screening: on admission and postoperatively.
· Nutrition screening: within 24–48 hours.
· Pressure-ulcer risk assessment and prevention plan documentation.
· Pharmacological or mechanical VTE prophylaxis plan documented unless contraindicated.
· Medication review: Prompt review of medications by a geriatrician or an internist for appropriateness and polypharmacy on admission within 48 hours from admission.
E. Operation choice and surgical-quality KPIs:
· Operation appropriate to the fracture type: Percentage receiving evidence-based fixation/arthroplasty according to the fracture pattern and patient fitness.
· Implant choice documentation: Percentage with documented implant type, fixation method, approach, and surgeon grade.
· Immediate mobilization and weight-bearing plan: Percentage operation notes specifying unrestricted/full weight bearing unless contraindicated.
· Reoperation rate: Reoperation within 30/120 days.
· Surgical-site infection rate: Deep/superficial infection within 30/90 days.
F. Anaesthesia and perioperative KPIs:
· ASA grade documented: Percentage with ASA grade recorded preoperatively.
· Choice of anaesthesia spinal vs general discussed when feasible: Percentage with anaesthetic plan documented.
· Postoperative acute pain plan documented: Percentage with documented multimodal analgesia plan.
G. Mobilisation, rehabilitation, and discharge KPIs:
· Out of bed by day 1 after surgery: Percentage mobilised out of bed by the first postoperative day, unless contraindicated.
· Weight-bearing status documented: Percentage with clear postoperative weight-bearing instruction.
· Discharge rehabilitation plan documented: Percentage discharged with a written rehab and follow-up plan.
· Return to original residence: Percentage of patients discharged back to original residence at 120-day follow-up.
H. Secondary fracture prevention KPIs:
· Osteoporosis risk assessment: Percentage of patients assessed for osteoporosis or fracture risk before discharge or within 12 weeks.
· Calcium/vitamin D status addressed: Percentage of patients with supplementation or documented contraindications/clinical decisions.
· Anti-osteoporosis medication started or planned: Percentage of eligible patients discharged on therapy or with a follow-up appointment.
· Falls risk assessment: Percentage of patients assessed for falls risk before discharge or within 12 weeks.
· Sarcopenia/nutrition intervention: Percentage of patients with nutrition/sarcopenia risk plans if abnormal.
I. Outcome KPIs:
· In-hospital mortality: Death before discharge.
· Length of hospital stay: Admission to discharge from acute care.
· 30-day readmission: Any unplanned readmission.
· Reoperation within 30/120 days: Any return to the operating room related to hip fracture surgery.
· Pressure ulcer during admission: New pressure ulcer after admission.
· Delirium incidence: New delirium during admission.
We can classify these KPIs into a three-level model:
Core mandatory KPIs:
· Case capture, surgery timing, medical review, mobilization, discharge status, and mortality.
Quality-improvement KPIs:
· Analgesia, delirium, nutrition, pressure ulcers, implant choice, and rehabilitation.
Secondary prevention KPIs:
· Osteoporosis treatment falls assessment and prevention.
- Research gaps
During the preparation of the above guidelines, the GDG have identified several gaps in current research and evidence-based literature. The following list is not exhaustive but could be useful to guide different scientific bodies (universities, research centres and healthcare organisations) in developing their research plans.
1. Epidemiology and National Burden in Egypt
Egypt has emerging data on hip-fracture incidence and geographic variation. However, there is still a lack of a comprehensive national hip-fracture registry that covers public, university, military, insurance, and private hospitals.
Key research gaps include:
· Determining the true national incidence of fragility hip fractures by governorate, sex, age group, and rural/urban residence.
· Developing national risk assessment tools to identify patients at risk of fractures early.
· Identifying seasonal variations, fall locations, mechanisms of injury, and delays in presentation.
· Assessing mortality rates after hip fractures in Egyptian patients at 30 days, 120 days, and 1 year.
· Collecting national data on return to mobility, return home, dependency, and caregiver burden.
· Understanding the cost of hip-fracture care in Egypt, including out-of-pocket expenses.
Possible research questions include:
· Determining the true annual incidence of low-energy hip fractures among Egyptians aged ≥60 or ≥65 years.
· Investigating whether outcomes differ between Upper Egypt and Lower Egypt.
· Assessing the proportion of patients who die within 30 days and 1 year after hip fractures in Egypt.
· Analysing the direct and indirect costs of hip-fracture care for Egyptian families.
2. Time-to-Surgery and Causes of Surgical Delay
Internationally, timely surgery is considered a crucial quality indicator. The World Health Organization (WHO) has proposed indicators focused on surgery within 48 hours and pharmacological osteoporosis treatment after hip fractures. The National Institute for Health and Care Excellence (NICE) recommends surgery on the day of admission or the day after.
Key research gaps include:
· Determining the actual time from admission to surgery in Egyptian hospitals.
· Identifying the medical and system-related causes of delays.
· Understanding the reasons behind delays due to factors such as theatre availability, implant availability, blood products, ICU beds, finance, consent, and anaesthesia clearance.
· Exploring the relationship between delays and mortality, complications, length of stay, and cost.
Possible research questions include:
· Determining the percentage of older Egyptian hip-fracture patients who receive surgery within 48 hours.
· What are the top five reasons for surgery after 48 hours?
· Are system delays more common than medical delays?
· Does a dedicated hip-fracture trauma list improve the time to surgery?
3. Orthogeriatric and multidisciplinary care gaps
Orthogeriatric care is widely recommended, but LMIC studies reveal that specialist orthogeriatric expertise is often unavailable, senior medical input is inconsistent, and care pathways vary significantly between institutions.
Key research gaps:
· Availability of geriatricians or internists for hip-fracture co-management in Egyptian hospitals.
· Effect of physician-led perioperative optimization on the time to surgery, delirium, medical complications, and mortality.
· Feasible Egyptian model: orthogeriatrician, internal medicine physician, anaesthetist-led optimization clinic, or nurse-led pathway.
· Role of multidisciplinary hip-fracture rounds.
Possible research questions:
· Does physician/geriatric co-management reduce complications in older Egyptian hip-fracture patients?
· What is the minimum feasible orthogeriatric model for Egyptian university hospitals?
· Can a structured multidisciplinary hip-fracture pathway reduce mortality and length of stay?
· What training do orthopaedic and medical residents need for geriatric trauma care?
· Can orthogeriatric care integration reduce cost of hip fractures in Egypt.
4. Pain management and regional nerve-block gaps
NICE recommends immediate analgesia, repeated pain assessment, and consideration of nerve blocks when analgesia is inadequate or to limit opioid use.
Key research gaps:
· Time to first analgesia in Egyptian emergency departments.
· Use of pain scores in cognitively intact versus impaired patients.
· Availability and effectiveness of fascia iliaca, femoral nerve, or PENG blocks.
· Impact of nerve blocks on opioid use, delirium, mobilization, and patient comfort.
Possible research questions:
· What proportion of hip-fracture patients receive analgesia within 30 minutes?
· Are regional blocks feasible in Egyptian emergency departments?
· Does fascia iliaca or PENG block reduce delirium or opioid requirement?
· Are pain scores reliably documented in older patients with cognitive impairment?
5. Surgical-treatment and implant-selection gaps.
Guidelines recommend procedure selection based on fracture type, pre-fracture function, and medical fitness. NICE recommends arthroplasty for displaced intracapsular fractures, cemented implants for arthroplasty, extramedullary fixation for most trochanteric fractures, and intramedullary fixation for subtrochanteric fractures.
Key research gaps include:
· Current implant choices in Egypt for displaced intracapsular, trochanteric, and subtrochanteric fractures.
· Cemented versus uncemented hemiarthroplasty outcomes in Egyptian patients.
· Use and outcomes of THA versus hemiarthroplasty in active older adults.
· Implant availability and cost-effectiveness.
· Reoperation, infection, dislocation, and peri-implant fracture rates.
Possible research questions include:
· What implants are actually used for hip fractures in Egyptian trauma centers?
· Is cemented hemiarthroplasty associated with better mobility and fewer reoperations in Egypt?
· Which Egyptian patients benefit from total hip arthroplasty after displaced femoral neck fracture?
· What is the reoperation rate after DHS, cephalomedullary nail, and hemiarthroplasty?
6. Anaesthesia and perioperative-risk gaps
NICE recommends offering spinal or general anaesthesia after discussing risks and benefits and considering intraoperative nerve blocks.
Key research gaps include:
· Spinal versus general anaesthesia outcomes in older Egyptian hip-fracture patients.
· Anaesthesia-related delay.
· Bone-cement implantation syndrome incidence and prevention.
· Perioperative protocols for anticoagulated patients.
· Availability of high-dependency or ICU beds for frail patients.
Possible research questions include:
· Does anaesthetic type influence delirium, hypotension, mortality, or mobilization?
· How often does anticoagulation delay surgery?
· What is the incidence of complications related to cement during hemiarthroplasty?
· Can a standard anticoagulation reversal protocol reduce the time to surgery?
7. Mobilization and rehabilitation gaps
NICE recommends physiotherapy assessment and mobilization on the day after surgery unless contraindicated, with daily mobilization thereafter. However, LMIC service-readiness work shows variation in mobilization and weight-bearing protocols.
Key research gaps:
· Availability of physiotherapy in Egyptian trauma wards, especially on weekends.
· Time to first mobilization after surgery.
· Barriers to mobilization, such as pain, fear, family reluctance, staffing, lack of walking aids, and surgeon restrictions.
· Effect of early mobilization on pneumonia, pressure ulcers, length of stay, and functional recovery.
· Post-discharge rehabilitation access.
Possible research questions:
· What percentage of Egyptian hip-fracture patients mobilize by postoperative day 1?
· What are the main barriers to early mobilization?
· Does early mobilization reduce length of stay and complications?
· Is a caregiver-assisted rehabilitation program feasible after discharge?
8. Osteoporosis and secondary-fracture prevention gaps
Egyptian data show a significant osteoporosis treatment gap. In a multicenter study, 82.1% of eligible postmenopausal women and 100% of eligible men were not receiving osteoporosis therapy before their index fragility fracture.
Key research gaps:
· Proportion of hip-fracture patients discharged on anti-osteoporosis medication.
· DXA access and whether DXA should delay treatment.
· Creating alternative osteoporosis screening methods in areas where DXA is not available (e.g.; calcaneal US)
· Use of vitamin D, calcium, bisphosphonates, denosumab, or anabolic therapy after hip fracture.
· Medication adherence at 6 and 12 months.
· Feasibility and effectiveness of Fracture Liaison Service models in Egypt.
Possible research questions:
· What proportion of Egyptian hip-fracture patients receive osteoporosis treatment after discharge?
· Does an FLS reduce secondary fractures and improve medication adherence?
· Is a “treat-first, DXA-later” strategy appropriate for Egyptian hip-fracture patients?
· What are the barriers to osteoporosis treatment in men after hip fracture?
9. Falls, sarcopenia, and frailty gaps
Egyptian osteoporosis-gap data revealed that falls, sarcopenia, and functional disability were significantly associated with fracture risk, underscoring the need for multifactorial prevention strategies rather than focusing solely on bone density.
Key research gaps include:
· Prevalence of sarcopenia and frailty among Egyptian hip-fracture patients.
· Validation of Arabic frailty and sarcopenia tools in acute trauma settings.
· Relationship between frailty, surgical delay, complications, and mortality.
· Effectiveness of nutrition, protein supplementation, vitamin D, and strength/balance training.
Possible research questions include:
· Which frailty score best predicts mortality after hip fracture in Egyptian patients?
· Is SARC-F a useful screening tool in Egyptian trauma wards?
· Does nutritional supplementation improve mobilization and recovery?
· Can falls-risk assessment reduce recurrent falls after hip fracture?
10. Nutrition and pressure-ulcer prevention gaps
The FFN’s minimum dataset includes pressure ulcer development during admission, while its extended dataset includes nutritional assessment because nutrition is a modifiable factor in hip-fracture recovery.
Key research gaps include:
· Malnutrition prevalence in older Egyptian hip-fracture patients.
· Use of nutritional screening tools such as MNA or MUST.
· Relationship between malnutrition and infection, pressure ulcers, delayed mobilization, and mortality.
· Frequency and severity of pressure ulcers on admission versus hospital-acquired ulcers.
Possible research questions include:
· What is the prevalence of malnutrition in older Egyptian hip-fracture patients?
· Does nutrition screening predict complications?
· Does early protein supplementation reduce pressure ulcers and length of stay?
· How many pressure ulcers are present on admission due to delayed presentation?
· What are the causes of delayed presentation in Egyptian population?
11. Patient-reported outcome and quality-of-life
Patient-reported outcome and quality-of-life gaps after geriatric hip fracture remain significant research areas. A systematic review revealed substantial heterogeneity in patient-reported outcome measures, poor reporting of missing data, inconsistent reporting of effect size, and inadequate interpretation of patient-reported outcomes.
Key research gaps include:
The development of Arabic-validated patient-reported outcomes (PROMs) for hip fracture recovery, identifying patient priorities after hip fracture, exploring quality-of-life outcomes beyond mortality, and investigating fear of falling and confidence levels after surgery.
Possible research questions
· Which Arabic PROM is most suitable for Egyptian hip-fracture patients?
· What outcomes do Egyptian patients and caregivers consider most important?
· Does early surgery improve quality of life at 120 days?
· How does fear of falling affect rehabilitation and return to independence?
- Update of the guideline
This guideline
will be updated whenever there is new evidence
- Annexes
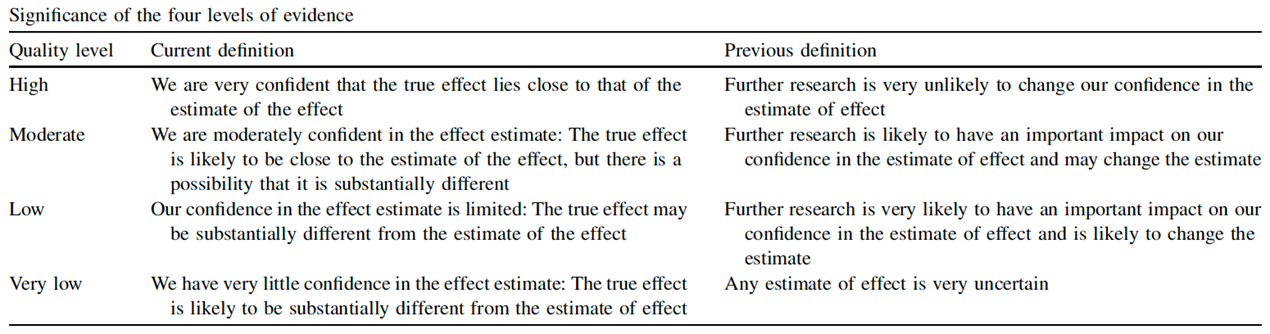
Annex 2: Minimum interruption intervals
(summary table)
These intervals apply to neuraxial and deep/non-compressible procedures. For superficial/compressible single-shot blocks, apply site-based risk assessment.
|
Drug (generic [trade]) |
Dose category (examples) |
Minimum hold before neuraxial/deep |
Superficial/compressible single-shot blocks |
|
LMWH: enoxaparin [Clexane/Lovenox]; dalteparin [Fragmin]; tinzaparin [Innohep]
|
Low dose (prophylaxis); e.g., enoxaparin ≤40 mg/day |
≥12 h (if CrCl <30: halve dose or extend to 24 h) |
May proceed; next dose at routine time (site-based risk assessment) |
|
High dose (>50 IU anti-Xa/kg/day or therapeutic); often BID |
≥24 h (if CrCl <30: halve dose or extend to 48 h) |
May proceed; next dose at routine time (site-based risk assessment) |
|
|
Unfractionated heparin (UFH) [Heparin]
|
Low-dose SC UFH (≤200 IU/kg/day) |
≥4 h |
May proceed; next dose at routine time (site-based risk assessment) |
|
High-dose UFH (IV or SC) |
IV: ≥6 h; SC: ≥12 h (or until aPTT/anti-Xa/ACT returns to local normal range) |
May proceed; next dose at routine time (site-based risk assessment) |
|
|
Fondaparinux [Arixtra]
|
Low dose (≤2.5 mg/day) |
≥36 h (if CrCl <50: ≥72 h) |
May proceed; next dose at routine time (site-based risk assessment) |
|
High dose (>2.5 mg/day) |
Not recommended; if unavoidable, consider ~4 days or level-guided (specialist decision) |
Site-based; consider alternative strategy |
|
|
Vitamin K antagonist: warfarin [Coumadin] |
Therapeutic |
Stop ~5 days; proceed when INR is normal/acceptable per local policy |
Site-based; deep/non-compressible sites require INR target |
|
Direct anti-Xa DOACs: rivaroxaban [Xarelto]; edoxaban [Lixiana/Savaysa]; apixaban [Eliquis]
|
Low dose |
Rivaroxaban/edoxaban: ≥24 h (≥30 h if CrCl <30); apixaban: ≥36 h |
May proceed; next dose at routine time (site-based risk assessment) |
|
High dose |
≥72 h (or level-guided in renal impairment where available) |
May proceed; next dose at routine time (site-based risk assessment) |
|
|
Direct thrombin inhibitor DOAC: dabigatran [Pradaxa]
|
Low dose |
≥48 h |
May proceed; next dose at routine time (site-based risk assessment) |
|
High dose |
≥72 h (or level-guided if CrCl <50) |
May proceed; next dose at routine time (site-based risk assessment) |
|
|
Aspirin [Aspirin]
|
Low dose (≤200 mg/day) |
No mandatory hold |
No mandatory hold |
|
High dose (≥200 mg/day) |
≥3 to 7 days |
Site-based; consider risk–benefit |
|
|
Clopidogrel [Plavix] |
P2Y12 inhibitor |
≥5 to 7 days |
Site-based; consider risk–benefit |
|
Ticagrelor [Brilinta] |
P2Y12 inhibitor |
≥5 days |
Site-based; consider risk–benefit |
|
Prasugrel [Effient] |
P2Y12 inhibitor |
≥7 days |
Site-based; consider risk–benefit |
Operational catheter notes (LMWH): once-daily prophylaxis: first LMWH dose ≥12 h after needle/catheter placement; remove catheter ≥12 h after last LMWH dose; next dose ≥4 h after catheter removal. Twice-daily prophylaxis: remove neuraxial catheter before initiating LMWH; delay LMWH ≥4 h after catheter removal; and if LMWH used >4 days, check platelet count before neuraxial/deep procedures or catheter removal.
Annex 3:
FLACC score and
Ramsay sedation score
FLACC Score
|
CATEGORY |
0 POINTS |
1 POINT |
2 POINTS |
|
Face |
Disinterested |
Occasional grimace, withdrawn |
Frequent frown, clenched jaw |
|
Legs |
No position or relaxed |
Uneasy, restless, tense |
Kicking or legs drawn up |
|
Activity |
Normal position |
Squirming, tense |
Arched, rigid, or jerking |
|
Cry |
No crying |
Moans or whimpers |
Constant crying, screams or sobs |
|
Consolability |
Content, relaxed |
Distractible |
Inconsolable |
Ramsay Sedation Score
|
Score |
Description |
|
1 |
Anxious and agitated or restless, or both |
|
2 |
Cooperative, orientated, and tranquil |
|
3 |
Drowsy, but responds to commands |
|
4 |
Asleep, brisk response to light glabellar tap or loud auditory stimulus |
|
5 |
Asleep, sluggish response to light glabellar tap or loud auditory stimulus |
|
6 |
Asleep and unarousable |
Annex 4: Multimodal analgesia for hip fracture
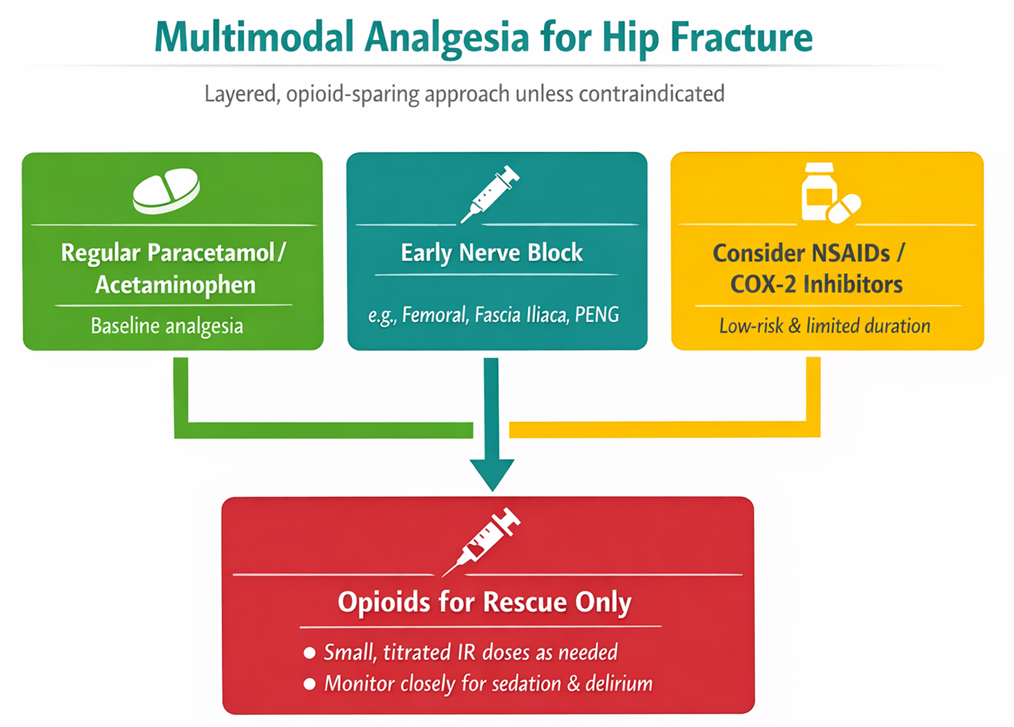
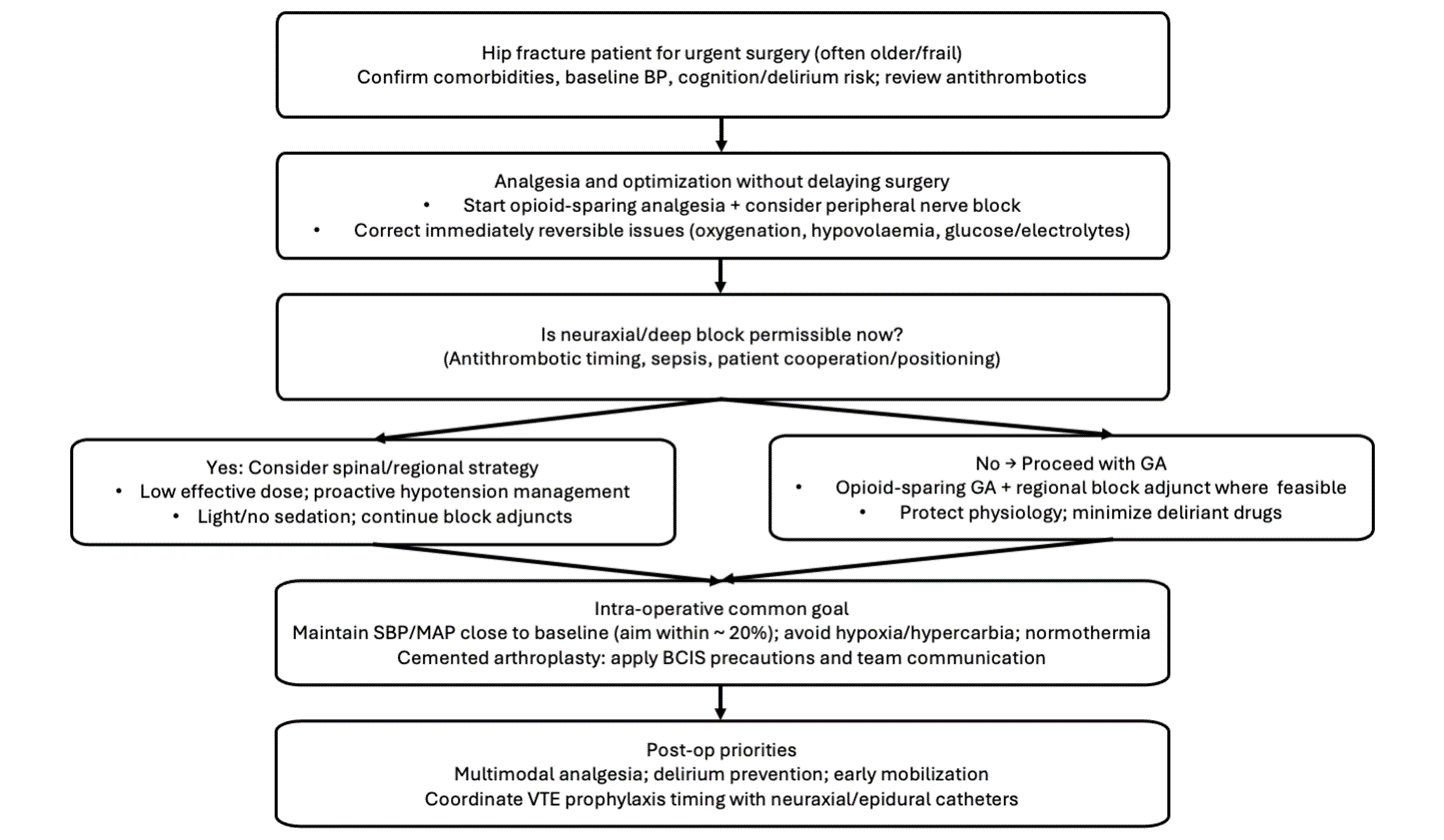
Annex 6: Garden Classification of Femoral Neck Fracture
|
Type |
Description |
Displacement |
Fracture Line |
Stability |
|
Type I |
Incomplete valgus impacted fracture |
None (impacted in valgus) |
Incomplete, doesn't traverse full width of neck |
Stable |
|
Type II |
Complete fracture |
Non |
fragments not displaced |
Stable |
|
Type III |
Complete fracture |
Partial displacement femoral head rotated into varus |
Complete, with partial displacement |
Unstable |
|
Type IV |
Complete fracture |
Complete displacement of femoral head |
Complete, totally displaced fragments |
Unstable |
Annex 7: Blood transfusion in elderly hip fracture patients (flowchart)
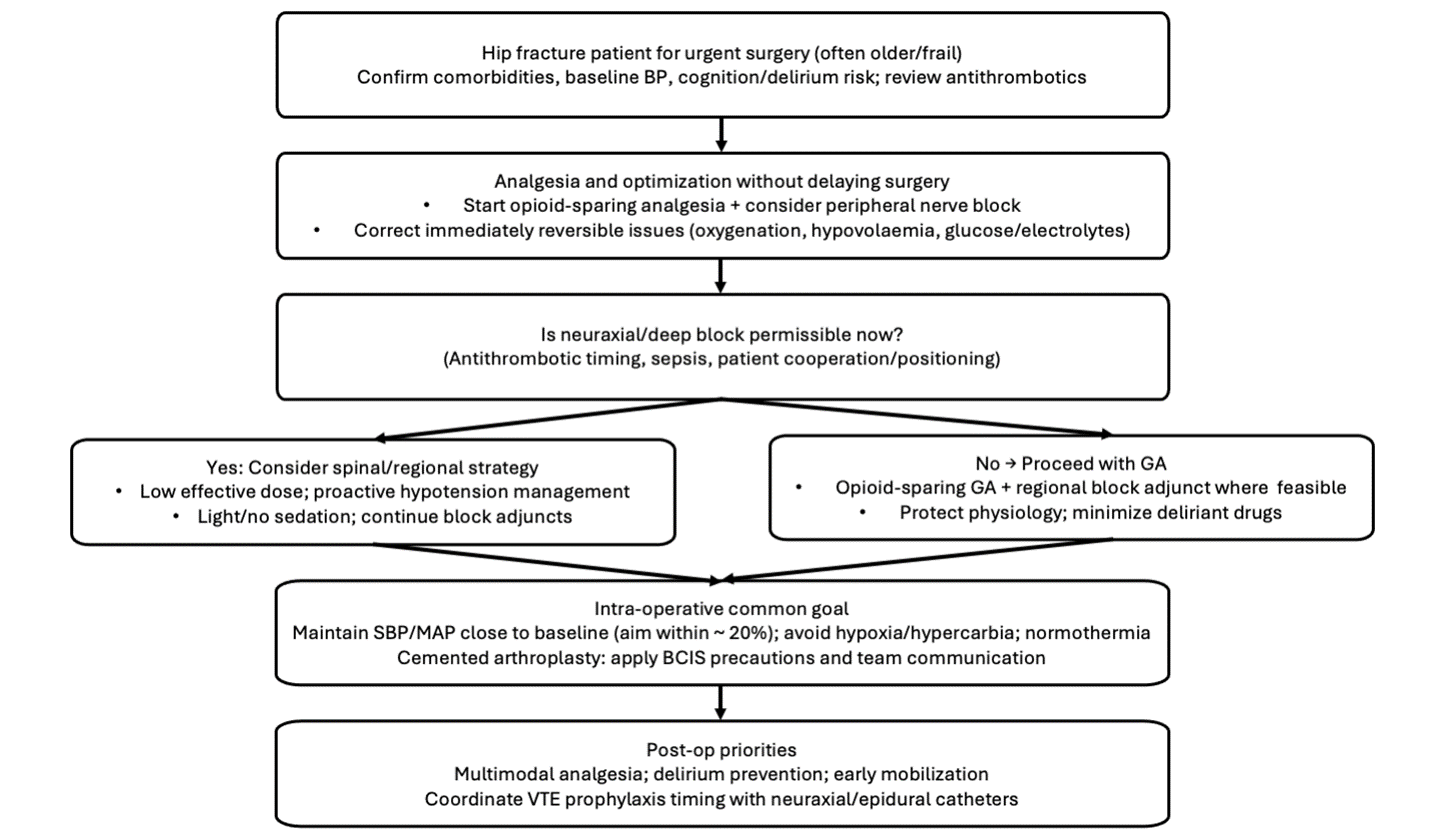
Annex 8: Tranexamic acid (TXA) in elderly hip fracture patients

- References
1. Ibrahim MA, Abdelzaher H, Alghamdi AA, Bakhaider AK, Farouk O, Abdelnasser MK. Encouraging recovery or avoiding risk? A proposed clinical framework for rehabilitation decision-making after fragility fractures. Injury 2026; 57(6): 113195.
2. O'Connor MI, Switzer JA. AAOS Clinical Practice Guideline Summary: Management of Hip Fractures in Older Adults. J Am Acad Orthop Surg 2022; 30(20): e1291–e6.
3. Brink O. Hip fracture clearance: How much optimisation is necessary? Injury 2020; 51 Suppl 2: S111–s7.
4. Verduijn WH, Sipers W, Spaetgens B. Optimizing Orthogeriatric Hip Fracture Care: Why Fracture Type Matters. J Am Med Dir Assoc 2024; 25(10): 105191.
5. Rivera F, Comba LC, Colombo M, Benazzo F, Cavaliere P, Solarino G. Management of intracapsular hip fracture: Current trends from a national survey. Injury 2024; 55: 111539.
6. Eardley W, Johansen A. Safety and efficacy in the management of older patients with displaced intracapsular hip fractures. Injury 2024; 55(7): 111598.
7. NICE.org.uk. Hip fracture management. 2025.
8. Balshem H, Helfand M, Schünemann HJ, et al. GRADE guidelines: 3. Rating the quality of evidence. J Clin Epidemiol 2011; 64(4): 401–6.
9. Qu H, Bian L. Comparison of CT and MRI in diagnosing occult hip fracture: a systematic review and meta-analysis. Am J Transl Res 2024; 16(7): 2745–55.
10. Hakkarinen DK, Banh KV, Hendey GW. Magnetic Resonance Imaging Identifies Occult Hip Fractures Missed by 64-slice Computed Tomography. The Journal of Emergency Medicine 2012; 43(2): 303–7.
11. Collin D, Geijer M, Göthlin JH. Computed tomography compared to magnetic resonance imaging in occult or suspect hip fractures. A retrospective study in 44 patients. Eur Radiol 2016; 26(11): 3932–8.
12. Macdonald H, Vetharajan N, Kempshall P. Patients with Clinically Suspected but Unproven Hip Fractures, Who Require Cross-Sectional Imaging, Are Best Initially Admitted under Geriatrician-Led Care-A Retrospective Review. Geriatrics (Basel) 2018; 3(4).
13. Endo J, Yamaguchi S, Saito M, et al. Efficacy of preoperative skin traction for hip fractures: a single-institution prospective randomized controlled trial of skin traction versus no traction. J Orthop Sci 2013; 18(2): 250–5.
14. Rosen JE, Chen FS, Hiebert R, Koval KJ. Efficacy of preoperative skin traction in hip fracture patients: a prospective, randomized study. J Orthop Trauma 2001; 15(2): 81–5.
15. Needoff M, Radford P, Langstaff R. Preoperative traction for hip fractures in the elderly: a clinical trial. Injury 1993; 24(5): 317–8.
16. Resch S, Bjärnetoft B, Thorngren KG. Preoperative skin traction or pillow nursing in hip fractures: a prospective, randomized study in 123 patients. Disabil Rehabil 2005; 27(18-19): 1191–5.
17. Resch S, Thorngren KG. Preoperative traction for hip fracture: a randomized comparison between skin and skeletal traction in 78 patients. Acta Orthop Scand 1998; 69(3): 277–9.
18. Saygi B, Ozkan K, Eceviz E, Tetik C, Sen C. Skin traction and placebo effect in the preoperative pain control of patients with collum and intertrochanteric femur fractures. Bull NYU Hosp Jt Dis 2010; 68(1): 15–7.
19. Tosun B, Aslan O, Tunay S. Preoperative position splint versus skin traction in patients with hip fracture: An experimental study. Int J Orthop Trauma Nurs 2018; 28: 8–15.
20. Yip DK, Chan CF, Chiu PK, Wong JW, Kong JK. Why are we still using pre-operative skin traction for hip fractures? Int Orthop 2002; 26(6): 361–4.
21. Seong YJ, Shin WC, Moon NH, Suh KT. Timing of Hip-fracture Surgery in Elderly Patients: Literature Review and Recommendations. Hip Pelvis 2020; 32(1): 11–6.
22. Shiga T, Wajima Z, Ohe Y. Is operative delay associated with increased mortality of hip fracture patients? Systematic review, meta-analysis, and meta-regression. Can J Anaesth 2008; 55(3): 146–54.
23. Moja L, Piatti A, Pecoraro V, et al. Timing matters in hip fracture surgery: patients operated within 48 hours have better outcomes. A meta-analysis and meta-regression of over 190,000 patients. PLoS One 2012; 7(10): e46175.
24. Simunovic N, Devereaux PJ, Sprague S, et al. Effect of early surgery after hip fracture on mortality and complications: systematic review and meta-analysis. Cmaj 2010; 182(15): 1609–16.
25. Kopp SL, Vandermeulen E, McBane RD, Perlas A, Leffert L, Horlocker T. Regional anesthesia in the patient receiving antithrombotic or thrombolytic therapy: American Society of Regional Anesthesia and Pain Medicine Evidence-Based Guidelines (fifth edition). Reg Anesth Pain Med 2025.
26. Kietaibl S, Ferrandis R, Godier A, et al. Regional anaesthesia in patients on antithrombotic drugs: Joint ESAIC/ESRA guidelines. Eur J Anaesthesiol 2022; 39(2): 100–32.
27. NICE.org.uk. Venous thromboembolism in over 16s reducing the risk of hospital acquired deep vein thrombosis or pulmonary embolism. 2018.
28. Guay J, Kopp S. Peripheral nerve blocks for hip fractures in adults. Cochrane Database of Systematic Reviews 2020; (11).
29. Sachdev D, Khalil L, Gendi K, et al. Perioperative Management of Traditional and Direct Oral Anticoagulants in Hip Fracture Patients. Orthop Rev (Pavia) 2024; 16: 115605.
30. Griffiths R, White SM, Moppett IK, et al. Safety guideline: reducing the risk from cemented hemiarthroplasty for hip fracture 2015: Association of Anaesthetists of Great Britain and Ireland British Orthopaedic Association British Geriatric Society. Anaesthesia 2015; 70(5): 623–6.
31. Merkel SI, Voepel-Lewis T, Shayevitz JR, Malviya S. The FLACC: a behavioral scale for scoring postoperative pain in young children. Pediatr Nurs 1997; 23(3): 293–7.
32. Ramsay MA, Savege TM, Simpson BR, Goodwin R. Controlled sedation with alphaxalone-alphadolone. Br Med J 1974; 2(5920): 656–9.
33. Griffiths R, Babu S, Dixon P, et al. Guideline for the management of hip fractures 2020: Guideline by the Association of Anaesthetists. Anaesthesia 2021; 76(2): 225–37.
34. (ESRA) PWG. Summary recommendations Hip fracture repair surgery, 2023.
35. El-Boghdadly K, Levy NA, Fawcett WJ, et al. Peri-operative pain management in adults: a multidisciplinary consensus statement from the Association of Anaesthetists and the British Pain Society. Anaesthesia 2024; 79(11): 1220–36.
36. Neuman MD, Feng R, Carson JL, et al. Spinal Anesthesia or General Anesthesia for Hip Surgery in Older Adults. N Engl J Med 2021; 385(22): 2025–35.
37. American Academy of Orthopaedic Surgeons Orthopaedic Education Study G. Management of Hip Fractures in Older Adults Evidence- Based Clinical Practice Guideline., 2021.
38. Basu N, Natour M, Mounasamy V, Kates SL. Geriatric hip fracture management: keys to providing a successful program. European Journal of Trauma and Emergency Surgery 2016; 42(5): 565–9.
39. Wenk M, Frey S. Elderly hip fracture patients: surgical timing and factors to consider. Current Opinion in Anesthesiology 2021; 34(1): 33–9.
40. Okike K, Udogwu UN, Isaac M, et al. Not All Garden-I and II Femoral Neck Fractures in the Elderly Should Be Fixed: Effect of Posterior Tilt on Rates of Subsequent Arthroplasty. J Bone Joint Surg Am 2019; 101(20): 1852–9.
41. Papadelis E, Chaudhry YP, Hayes H, Talone C, Shah MP. Evaluation of the Posterior Tilt Angle in Predicting Failure of Nondisplaced Femoral Neck Fractures After Internal Fixation: A Systematic Review. J Orthop Trauma 2023; 37(2): e89–e94.
42. Dolatowski FC, Frihagen F, Bartels S, et al. Screw Fixation Versus Hemiarthroplasty for Nondisplaced Femoral Neck Fractures in Elderly Patients: A Multicenter Randomized Controlled Trial. J Bone Joint Surg Am 2019; 101(2): 136–44.
43. Ma H-H, Chou T-FA, Tsai S-W, Chen C-F, Wu P-K, Chen W-M. Outcomes of internal fixation versus hemiarthroplasty for elderly patients with an undisplaced femoral neck fracture: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research 2019; 14(1): 320.
44. Ekhtiari S, Gormley J, Axelrod DE, Devji T, Bhandari M, Guyatt GH. Total Hip Arthroplasty Versus Hemiarthroplasty for Displaced Femoral Neck Fracture: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. J Bone Joint Surg Am 2020; 102(18): 1638–45.
45. Parker MJ, Gurusamy K. Internal fixation versus arthroplasty for intracapsular proximal femoral fractures in adults. Cochrane Database Syst Rev 2006; 2006(4): Cd001708.
46. Wang J, Jiang B, Marshall RJ, Zhang P. Arthroplasty or internal fixation for displaced femoral neck fractures: which is the optimal alternative for elderly patients? A meta-analysis. Int Orthop 2009; 33(5): 1179–87.
47. Bloemheuvel EM, van Steenbergen LN, Swierstra BA, Schreurs BW. Revision Risk of Unipolar and Bipolar Hemiarthroplasties in the Dutch Arthroplasty Register. J Arthroplasty 2024; 39(1): 118–23.
48. Calder SJ, Anderson GH, Jagger C, Harper WM, Gregg PJ. Unipolar or bipolar prosthesis for displaced intracapsular hip fracture in octogenarians: a randomised prospective study. J Bone Joint Surg Br 1996; 78(3): 391–4.
49. Cornell CN, Levine D, O'Doherty J, Lyden J. Unipolar versus bipolar hemiarthroplasty for the treatment of femoral neck fractures in the elderly. Clin Orthop Relat Res 1998; (348): 67–71.
50. Davison JN, Calder SJ, Anderson GH, et al. Treatment for displaced intracapsular fracture of the proximal femur. A prospective, randomised trial in patients aged 65 to 79 years. J Bone Joint Surg Br 2001; 83(2): 206–12.
51. Jeffcote B, Li MG, Barnet-Moorcroft A, Wood D, Nivbrant B. Roentgen stereophotogrammetric analysis and clinical assessment of unipolar versus bipolar hemiarthroplasty for subcapital femur fracture: a randomized prospective study. ANZ J Surg 2010; 80(4): 242–6.
52. Malhotra R, Arya R, Bhan S. Bipolar hemiarthroplasty in femoral neck fractures. Arch Orthop Trauma Surg 1995; 114(2): 79–82.
53. Raia FJ, Chapman CB, Herrera MF, Schweppe MW, Michelsen CB, Rosenwasser MP. Unipolar or bipolar hemiarthroplasty for femoral neck fractures in the elderly? Clin Orthop Relat Res 2003; (414): 259–65.
54. Tang X, Wang D, Liu Y, et al. The comparison between total hip arthroplasty and hemiarthroplasty in patients with femoral neck fractures: a systematic review and meta-analysis based on 25 randomized controlled trials. Journal of Orthopaedic Surgery and Research 2020; 15.
55. Edelstein AI, Dillingham TR, McGinley EL, Pezzin LE. Hemiarthroplasty Versus Total Hip Arthroplasty for Femoral Neck Fracture in Elderly Patients: Twelve-Month Risk of Revision and Dislocation in an Instrumental Variable Analysis of Medicare Data. J Bone Joint Surg Am 2023; 105(21): 1695–702.
56. Falótico G, Matsunaga F, Sayum Filho J, et al. Total hip arthroplasty versus hemiarthroplasty for displaced femoral neck fracture: an overview of systematic reviews total hip arthroplasty versus hemiarthroplasty for displaced femoral neck fracture: an overview of systematic reviews. Journal of Orthopaedic Surgery and Research 2025; 20.
57. Chammout G, Kelly-Pettersson P, Hedbeck CJ, Stark A, Mukka S, Sköldenberg O. HOPE-Trial: Hemiarthroplasty Compared with Total Hip Arthroplasty for Displaced Femoral Neck Fractures in Octogenarians: A Randomized Controlled Trial. JB JS Open Access 2019; 4(2): e0059.
58. Bhandari M, Einhorn TA, Guyatt G, et al. Total Hip Arthroplasty or Hemiarthroplasty for Hip Fracture. N Engl J Med 2019; 381(23): 2199–208.
59. McCafferty J, Bragg J, Quindlen K, et al. Hip Hemiarthroplasty vs Total Hip Arthroplasty for Femoral Neck Fractures: Reverse Fragility of Reoperation Rates in Randomized Controlled Trials. Arthroplasty Today 2025; 35: 101805.
60. Burgers PT, Van Geene AR, Van den Bekerom MP, et al. Total hip arthroplasty versus hemiarthroplasty for displaced femoral neck fractures in the healthy elderly: a meta-analysis and systematic review of randomized trials. Int Orthop 2012; 36(8): 1549–60.
61. Yu L, Wang Y, Chen J. Total hip arthroplasty versus hemiarthroplasty for displaced femoral neck fractures: meta-analysis of randomized trials. Clin Orthop Relat Res 2012; 470(8): 2235–43.
62. Ramsay N, Close JCT, Harris IA, Harvey LA. The impact of cement fixation on early mortality in arthroplasty for hip fracture. Bone Jt Open 2023; 4(3): 198–204.
63. Roberts KC, Brox WT, Jevsevar DS, Sevarino K. Management of hip fractures in the elderly. J Am Acad Orthop Surg 2015; 23(2): 131–7.
64. Group AS. Australian and New Zealand Hip Fracture Registry. Annual report of hip fracture care 2025, September 2025.
65. Griffiths R, Parker M. Bone cement implantation syndrome and proximal femoral fracture. Br J Anaesth 2015; 114(1): 6–7.
66. Hines C. Understanding Bone Cement Implantation Syndrome. AANA Journal 2018; 86: 433–41.
67. Kristensen TB, Dybvik E, Kristoffersen M, et al. Cemented or Uncemented Hemiarthroplasty for Femoral Neck Fracture? Data from the Norwegian Hip Fracture Register. Clin Orthop Relat Res 2020; 478(1): 90–100.
68. Fernandez MA, Achten J, Parsons N, et al. Cemented or Uncemented Hemiarthroplasty for Intracapsular Hip Fracture. N Engl J Med 2022; 386(6): 521–30.
69. Ugland TO, Haugeberg G, Svenningsen S, et al. Biomarkers of muscle damage increased in anterolateral compared to direct lateral approach to the hip in hemiarthroplasty: no correlation with clinical outcome : Short-term analysis of secondary outcomes from a randomized clinical trial in patients with a displaced femoral neck fracture. Osteoporos Int 2018; 29(8): 1853–60.
70. Jianbo J, Ying J, Xinxin L, Lianghao W, Baoqing Y, Rongguang A. Hip hemiarthroplasty for senile femoral neck fractures: Minimally invasive SuperPath approach versus traditional posterior approach. Injury 2019; 50(8): 1452–9.
71. Li J, Xiao J, Zhang Z, Jia F, Wu Z. A Novel Fast Mobile-Window Small Incision Technique for Hip Arthroplasty in the Elderly and Comparison with Conventional Incision. Med Sci Monit 2017; 23: 3303–10.
72. Parker MJ, Griffiths R. General versus regional anaesthesia for hip fractures. A pilot randomised controlled trial of 322 patients. Injury 2015; 46(8): 1562–6.
73. Repantis T, Bouras T, Korovessis P. Comparison of minimally invasive approach versus conventional anterolateral approach for total hip arthroplasty: a randomized controlled trial. Eur J Orthop Surg Traumatol 2015; 25(1): 111–6.
74. Saxer F, Studer P, Jakob M, et al. Minimally invasive anterior muscle-sparing versus a transgluteal approach for hemiarthroplasty in femoral neck fractures-a prospective randomised controlled trial including 190 elderly patients. BMC Geriatr 2018; 18(1): 222.
75. Ugland TO, Haugeberg G, Svenningsen S, et al. High risk of positive Trendelenburg test after using the direct lateral approach to the hip compared with the anterolateral approach: a single-centre, randomized trial in patients with femoral neck fracture. Bone Joint J 2019; 101-b(7): 793–9.
76. Verzellotti S, Candrian C, Molina M, Filardo G, Alberio R, Grassi FA. Direct anterior versus posterolateral approach for bipolar hip hemiarthroplasty in femoral neck fractures: a prospective randomised study. Hip Int 2020; 30(6): 810–7.
77. Biber R, Brem M, Singler K, Moellers M, Sieber C, Bail HJ. Dorsal versus transgluteal approach for hip hemiarthroplasty: an analysis of early complications in seven hundred and four consecutive cases. Int Orthop 2012; 36(11): 2219–23.
78. Sköldenberg O, Ekman A, Salemyr M, Bodén H. Reduced dislocation rate after hip arthroplasty for femoral neck fractures when changing from posterolateral to anterolateral approach. Acta Orthop 2010; 81(5): 583–7.
79. Parker MJ, Bowers TR, Pryor GA. Sliding hip screw versus the Targon PF nail in the treatment of trochanteric fractures of the hip: a randomised trial of 600 fractures. J Bone Joint Surg Br 2012; 94(3): 391–7.
80. Cai L, Wang T, Di L, Hu W, Wang J. Comparison of intramedullary and extramedullary fixation of stable intertrochanteric fractures in the elderly: a prospective randomised controlled trial exploring hidden perioperative blood loss. BMC Musculoskelet Disord 2016; 17(1): 475.
81. Lewis SR, Macey R, Lewis J, et al. Surgical interventions for treating extracapsular hip fractures in older adults: a network meta-analysis. Cochrane Database Syst Rev 2022; 2(2): Cd013405.
82. Zhong B, Zhang Y, Zhang C, Luo CF. A comparison of proximal femoral locking compression plates with dynamic hip screws in extracapsular femoral fractures. Orthop Traumatol Surg Res 2014; 100(6): 663–8.
83. Zeelenberg ML, Plaisier AC, Nugteren LHT, et al. Extramedullary versus intramedullary fixation of unstable trochanteric femoral fractures (AO type 31-A2): a systematic review and meta-analysis. Arch Orthop Trauma Surg 2024; 144(3): 1189–209.
84. Kassem E, Younan R, Abaskhron M, Abo-Elsoud M. Functional and radiological outcomes of dynamic hip screw with trochanteric stabilizing plate versus short proximal femoral nail in management of unstable trochanteric fractures: A randomized-controlled trial. Jt Dis Relat Surg 2022; 33(3): 531–7.
85. Zhang S, Ge Y, Bi Z, et al. Implants for fixation of intertrochanteric femoral fracture: a systematic review and network meta-analysis of randomized controlled trials. BMC Musculoskelet Disord 2025; 26(1): 818.
86. Xie H, Xie L, Wang J, Chen C, Zhang C, Zheng W. Intramedullary versus extramedullary fixation for the treatment of subtrochanteric fracture: A systematic review and meta-analysis. Int J Surg 2019; 63: 43–57.
87. Wang J, Li H, Jia H, Ma X. Intramedullary versus extramedullary fixation in the treatment of subtrochanteric femur fractures: A comprehensive systematic review and meta-analysis. Acta Orthop Traumatol Turc 2020; 54(6): 639–46.
88. Keny S, Sharma G, Poduval M, Tiwari A, Bagaria V. Consensus-based guidelines on subtrochanteric femur fractures: Bridging evidence and experience on 11 key clinical dilemmas. Sicot j 2025; 11: 58.
89. Zerah L, Dourthe L, Cohen-Bittan J, et al. Retrospective Evaluation of a Restrictive Transfusion Strategy in Older Adults with Hip Fracture. J Am Geriatr Soc 2018; 66(6): 1151–7.
90. Soiza R, Myint P. The Scottish Intercollegiate Guidelines Network (SIGN) 157: Guidelines on Risk Reduction and Management of Delirium. Medicina 2019; 55: 491.
91. NICE.org.uk. Blood transfusion. 2015.
92. Carson JL, Terrin ML, Noveck H, et al. Liberal or restrictive transfusion in high-risk patients after hip surgery. N Engl J Med 2011; 365(26): 2453–62.
93. Carson JL, Guyatt G, Heddle NM, et al. Clinical Practice Guidelines From the AABB: Red Blood Cell Transfusion Thresholds and Storage. JAMA : the journal of the American Medical Association 2016; 316(19): 2025–35.
94. Chand NK, Subramanya HB, Rao GV. Management of patients who refuse blood transfusion. Indian J Anaesth 2014; 58(5): 658–64.
95. Canillas F, Gómez-Ramírez S, García-Erce JA, Pavía-Molina J, Gómez-Luque A, Muñoz M. "Patient blood management" in orthopaedic surgery. Rev Esp Cir Ortop Traumatol 2015; 59(3): 137–49.
96. Zufferey PJ, Miquet M, Quenet S, et al. Tranexamic acid in hip fracture surgery: a randomized controlled trial. Br J Anaesth 2010; 104(1): 23–30.
97. Practice guidelines for perioperative blood management: an updated report by the American Society of Anesthesiologists Task Force on Perioperative Blood Management*. Anesthesiology 2015; 122(2): 241–75.
98. Shander A, Bracey AW, Jr., Goodnough LT, et al. Patient Blood Management as Standard of Care. Anesth Analg 2016; 123(4): 1051–3.
99. Fillingham YA, Ramkumar DB, Jevsevar DS, et al. The Safety of Tranexamic Acid in Total Joint Arthroplasty: A Direct Meta-Analysis. J Arthroplasty 2018; 33(10): 3070–82.e1.
100. Ilic I, Stojadinovic I, Ristic B, Ilic M. Tranexamic Acid for Reduction of Blood Loss in Patients with Extracapsular Proximal Femur Fractures: Systematic Review and Meta-Analysis of Randomized Clinical Trials. Pharmaceutics 2026; 18(3).
101. Haj-Younes B, Sivakumar BS, Wang M, An VV, Lorentzos P, Adie S. Tranexamic acid in hip fracture surgery: A systematic review and meta-analysis. J Orthop Surg (Hong Kong) 2020; 28(1): 2309499019887995.
102. Shakur H, Roberts I, Bautista R, et al. Effects of tranexamic acid on death, vascular occlusive events, and blood transfusion in trauma patients with significant haemorrhage (CRASH-2): a randomised, placebo-controlled trial. Lancet 2010; 376(9734): 23–32.
103. Chen F, Jiang Z, Li M, Zhu X. Efficacy and safety of perioperative tranexamic acid in elderly patients undergoing trochanteric fracture surgery: a randomised controlled trial. Hong Kong Med J 2019; 25(2): 120–6.
104. Liu W, Deng S, Liang J. Tranexamic acid usage in hip fracture surgery: a meta-analysis and meta-regression analysis of current practice. Arch Orthop Trauma Surg 2022; 142(10): 2769–89.
105. Farrow L, Smith T, Ashcroft G, Myint P. A systematic review of Tranexamic acid in hip fracture surgery. British Journal of Clinical Pharmacology 2016; 82.
106. Poeran J, Rasul R, Suzuki S, et al. Tranexamic acid use and postoperative outcomes in patients undergoing total hip or knee arthroplasty in the United States: retrospective analysis of effectiveness and safety. Bmj 2014; 349: g4829.
107. Ker K, Edwards P, Perel P, Shakur H, Roberts I. Effect of tranexamic acid on surgical bleeding: systematic review and cumulative meta-analysis. Bmj 2012; 344: e3054.
108. Grigoryan KV, Javedan H, Rudolph JL. Orthogeriatric care models and outcomes in hip fracture patients: a systematic review and meta-analysis. J Orthop Trauma 2014; 28(3): e49–55.
109. Swift C, Ftouh S, Langford P, Chesser TS, Johanssen A. Interdisciplinary management of hip fracture. Clinical Medicine 2016; 16(6): 541–4.
110. Handoll HH, Cameron ID, Mak JC, Panagoda CE, Finnegan TP. Multidisciplinary rehabilitation for older people with hip fractures. Cochrane Database Syst Rev 2021; 11(11): Cd007125.
111. Baroni M, Serra R, Boccardi V, et al. The orthogeriatric comanagement improves clinical outcomes of hip fracture in older adults. Osteoporos Int 2019; 30(4): 907–16.
112. Ståhl A, Westerdahl E. Postoperative Physical Therapy to Prevent Hospital-acquired Pneumonia in Patients Over 80 Years Undergoing Hip Fracture Surgery-A Quasi-experimental Study. Clin Interv Aging 2020; 15: 1821–9.
113. Sarkies MN, Testa L, Carrigan A, et al. Perioperative interventions to improve early mobilisation and physical function after hip fracture: a systematic review and meta-analysis. Age Ageing 2023; 52(8).
114. Mazarello Paes V, Ting A, Masters J, Paes MVI, Graham SM, Costa ML. A systematic review of evidence regarding the association between time to mobilization following hip fracture surgery and patient outcomes. Bone Jt Open 2025; 6(7): 741–7.
115. Turabi RY, Sheehan KJ, Guerra S, O'Connell MDL, Wyatt D. Barriers and facilitators to early mobilisation and weight-bearing as tolerated after hip fracture surgery among older adults in Saudi Arabia: a qualitative study. Age Ageing 2024; 53(4).
116. Li N, Cheng KY, Zhang J, et al. Immediate weight bearing as tolerated versus delayed weight bearing following intramedullary fixation for geriatric intertrochanteric fractures: a post hoc analysis. BMC Musculoskelet Disord 2024; 25(1): 1041.
117. Warren J, Sundaram K, Anis H, et al. The association between weight-bearing status and early complications in hip fractures. Eur J Orthop Surg Traumatol 2019; 29(7): 1419–27.
118. Pfeufer D, Zeller A, Mehaffey S, Böcker W, Kammerlander C, Neuerburg C. Weight-bearing restrictions reduce postoperative mobility in elderly hip fracture patients. Arch Orthop Trauma Surg 2019; 139(9): 1253–9.
119. Ottesen TD, McLynn RP, Galivanche AR, et al. Increased complications in geriatric patients with a fracture of the hip whose postoperative weight-bearing is restricted: an analysis of 4918 patients. Bone Joint J 2018; 100-b(10): 1377–84.
120. Mallinson T, Deutsch A, Bateman J, et al. Comparison of discharge functional status after rehabilitation in skilled nursing, home health, and medical rehabilitation settings for patients after hip fracture repair. Arch Phys Med Rehabil 2014; 95(2): 209–17.
121. Soukkio PK, Suikkanen SA, Aartolahti EM, et al. Effects of Home-Based Physical Exercise on Days at Home, Health Care Utilization, and Functional Independence Among Patients With Hip Fractures: A Randomized Controlled Trial. Arch Phys Med Rehabil 2021; 102(9): 1692–9.
122. Rocha P, Baixinho CL, Marques A, Henriques MA. Safety-promoting interventions for the older person with hip fracture on returning home: A systematic review. Int J Orthop Trauma Nurs 2024; 52: 101063.
123. Ahmed Z, Ali MN, Riaz S. Outcome of fixation of comminuted and unstable intertrochanteric and sub-trochanteric femoral fractures by using proximal femoral locking plate. Medical Forum Monthly 2019; 30(2): 19–22.
124. Montero-Odasso M, van der Velde N, Martin FC, et al. World guidelines for falls prevention and management for older adults: a global initiative. Age Ageing 2022; 51(9).
125. Exter SH, Koenders N, Wees P, Berg MGA. A systematic review of the psychometric properties of physical performance tests for sarcopenia in community-dwelling older adults. Age Ageing 2024; 53(6).
126. McDonough CM, Harris-Hayes M, Kristensen MT, et al. Physical Therapy Management of Older Adults With Hip Fracture. J Orthop Sports Phys Ther 2021; 51(2): Cpg1–cpg81.
127. Ko Y, Hwang JM, Baek SH. Discharge transitional care programme for older adults after hip fracture surgery: a quasi-experimental study. J Res Nurs 2023; 28(8): 582–93.
128. Welsh A, Hanson S, Pfeiffer K, et al. Facilitating the transition from hospital to home after hip fracture surgery: a qualitative study from the HIP HELPER trial. BMC Geriatr 2024; 24(1): 948.
129. Sehgal M, Jacobs J, Biggs WS. Mobility Assistive Device Use in Older Adults. Am Fam Physician 2021; 103(12): 737–44.
130. Nahm ES, Resnick B, Orwig D, Magaziner J, Degrezia M. Exploration of informal caregiving following hip fracture. Geriatr Nurs 2010; 31(4): 254–62.
131. Magaziner J, Hawkes W, Hebel JR, et al. Recovery From Hip Fracture in Eight Areas of Function. The Journals of Gerontology: Series A 2000; 55(9): M498–M507.
132. MacLeod M, Chesson RA, Blackledge P, Hutchison JD, Ruta N. To what extent are carers involved in the care and rehabilitation of patients with hip fracture? Disability and Rehabilitation 2005; 27(18-19): 1117–22.
133. Barnett G, Swart M. Shared decision making for high-risk surgery. BJA Educ 2021; 21(8): 300–6.